Thursday, March 28, 2024

Parent to Child Transmission of Drug and Alcohol Abuse: A Narrative Review - Juniper Publishers

 Pediatrics & Neonatology - Juniper Publishers

Abstract

Introduction: Substance misuse, including alcohol and drug use, poses a major public health concern. One overlooked aspect is its transmission from parents to children, leading to multiple disorders and increasing societal prevalence. Parents significantly influence their child's development, with literature revealing a strong familial association of drug abuse transmission. This article aims to explore this issue, identify knowledge gaps, and propose avenues for further investigation, aiding evidence-based interventions, and prevention.

Materials and Methods: A comprehensive search of literature from 2015 to 2022 was conducted using PubMed and Scopus databases. Studies focused on substance abuse and alcohol transmission from parents to offspring. Screening criteria included study design, parental and offspring variables, and specific outcome terms.

Results: The global rise in drug and alcohol misuse has significant long-term and immediate consequences. Factors contributing to this phenomenon include high-stress environments, peer pressure, inadequate parental care, and family instability. Establishing drug rehabilitation centers in key urban areas is essential for treatment and awareness campaigns.

Conclusion: This analysis reveals that parental drug abuse is linked to various behaviors in children, including attention issues, academic underachievement, criminal behavior, and depression. More research is needed to understand the genetic and environmental factors involved in transmission.

Keywords: Drug abuse; Alcohol use disorder; Psychology; Substance misuse; Transmission of psychopathology

Abbreviations: AUD: Alcohol Use Disorder; DA: Drug Addiction; CUD: Cannabis Use Disorder; UNODC: UN Office on Drugs and Crime; SUDs: Substance Use Disorders

Introduction

Substance misuse, encompassing alcohol consumption, drug use, and other harmful behaviors, is a significant public health concern necessitating appropriate attention. An overlooked aspect is its potential transmission from parents to children, leading to multiple disorders and increasing societal prevalence. Parents play a pivotal role in their child's development, directly or indirectly influencing transmission. Literature reveals a robust familial association of drug abuse transmission via a temporal contagion model, with correlated risk linked to geographical proximity [1]. Furthermore, factors such as peer pressure, lifestyle habits, and environmental influences, including experiences of childhood loneliness and neglect, significantly contribute to the development of substance use disorders in individuals [2]. The susceptibility of young adults to alcohol-related issues may be influenced by genes involved in crucial processes within the nervous system, such as neurogenesis and signal transduction. Extensive research has examined various substances in the context of parent-child transmission. The risk of early alcohol initiation in children was found to be twofold higher when fathers engaged in alcohol and marijuana use, with an additive effect when mothers used tobacco.

Consequently, it has become imperative to delve into the transmission of alcohol and substance use from parents to offspring to gain a deeper understanding of the underlying mechanisms and develop more effective prevention and treatment strategies. However, to date, no comprehensive study has provided detailed insights into the modes of transmission and the most efficacious interventions to curtail it. This article aims to address this gap by comprehensively exploring every relevant aspect pertaining to the prevention of parent-to-child transmission of drug misuse [3,4]. The objectives of this article encompass assessing the current state of research on the transmission of drug and alcohol misuse from parents to children, identifying knowledge gaps, and proposing avenues for further investigation. By undertaking such an endeavor, we aim to enhance our understanding of this critical issue and provide valuable insights for the development of evidence-based interventions and preventive measures.

Methods

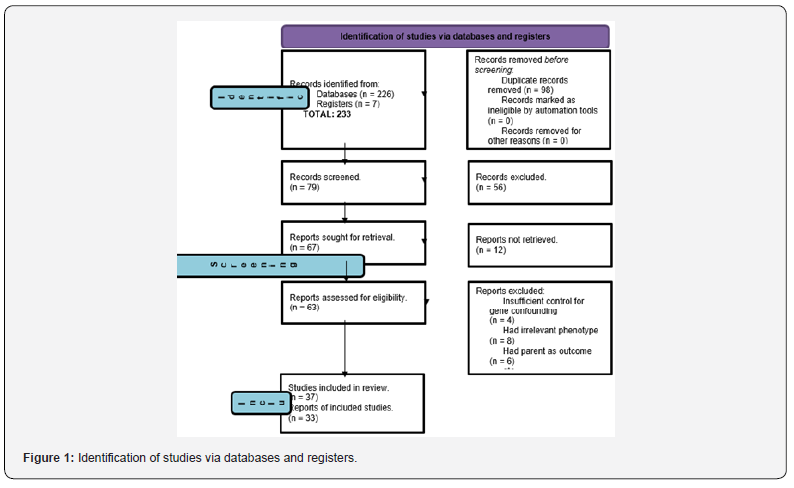
Analysis was done on literature available concerning substance abuse and the use of alcohol transmitted from parents to offspring. Studies that were published between 2015-2022 were taken from PubMed and Scopus databases using a systematic search. The terms used for screening comprised of variables relating to study design such as “multiple-parenting relationships'', “adoption”, “triparental”; parent terms like “father”, “parent”, “mother”, “paternal”, “maternal”; offspring variables which included “child”, “offspring” and finally topic terms such as “drug”, “substance”, “alcohol”. Search words that were outcome-specific were searched in order to limit our review to a distinct set of characteristic traits. Furthermore, the search was restricted to scientific articles that were published in English. Articles were obtained that yielded 233 results. After the removal of duplicates, our overall search gave 135 hits. The references in each of the articles selected from the preliminary search were also reviewed to select any article that further highlighted and gave a deeper insight into the topic. In this review, 37 articles were included. Children's ages ranged from 0 months to 21 years. This narrative review exclusively incorporates studies that adhere to the following criteria: (1) a comparison between parental traits and offspring performance, (2) utilization of an informative design that is genetically derived, and (3) an assessment of children's phenotype related to substance abuse, alcohol use, or associated traits (Figure 1).
Types of Substance Abuse

Through adolescence and into early adulthood, there is an increasing prevalence of both legal and illegal drug use, and substance abuse disorders often start in late youth or early adulthood [5]. Substances that are typically abused include:

i. Alcohol

ii. Opioid (heroin, fentanyl, prescription painkillers)

iii. Stimulants (cocaine, methamphetamine)

iv. Depressants (benzodiazepines, barbiturates)

v. Hallucinogens (LSD, psilocybin mushrooms)

vi. Cannabis(marijuana)

vii. Anabolic steroids

viii. Inhalants (solvents, aerosols, gasses, tobacco)

ix. Prescription drugs if taken in a manner or dose other than prescribed.

According to research findings, there is a suggestion that fathers who engage in alcohol, marijuana, and tobacco use during their adolescence exhibit a higher likelihood of having partners who are also involved in such practices [6]. This indicates that adults experiencing social and behavioral development challenges may be inclined to choose vulnerable partners, thereby transmitting the adverse effects of substance abuse to future generations through risky social associations [7]. Parental practices such as modeling substance abuse, poor communication, and monitoring have been shown to have a significant impact on a child’s substance abuse in adolescence. Studies have found that a parent’s history of substance use can predict these factors, leading to a high degree of congruence between a parent’s and child’s substance use behaviors [8-10]. Empirical evidence suggests that younger generations are initiating alcohol use at a later stage in life compared to their fathers. Notably, this trend appears to be more prominent among daughters than sons, potentially reflecting variations in cultural and social expectations across genders. It has been observed that younger generations are commencing tobacco use at a later stage than their fathers, potentially attributed to heightened awareness of the health hazards associated with tobacco consumption. This shift in behavior may also be influenced by distinct marketing and advertising strategies tailored to different age groups [6].

Association Between Father and Mother on Substance Use Disorders

Research indicates a significant association between substance use disorders (SUDs) in parents and their offspring, particularly in relation to drug and alcohol use. The dynamics of parents' relationships, including divorce, directly or indirectly influence a child's propensity for substance use. Divorce, specifically, has been linked to a heightened risk of drug use and can impede effective parenting practices. The association between divorce/separation and increased substance use underscores the psychological and social risks faced by children in such circumstances [11-12]. Studies have shown that children’s marijuana, tobacco, and alcohol use by early teenage years was predicted greatly by the fathers’ substance use compared to mothers’ [6,13]. The findings suggest that fathers' substance use exerts a stronger influence on children's own substance use. This may be attributed to the role of fathers in setting behavioral examples for their children. Consequently, there exists a substantial correlation between paternal lifetime cannabis use disorder (CUD) and the subsequent alcohol and cannabis usage of their offspring [14]. Additionally, a Swedish study found that parents who had AUD problems gave rise to offspring with increased chances of death, and death rates were higher when mothers had AUD issues [15]. There is an observed positive correlation between maternal alcohol use during pregnancy and the presence of ADHD in children. Additionally, maternal alcohol use can have adverse effects on the emotional and cognitive outcomes of the child [16]. However, higher maternal education and being in a current relationship with the child's biological father do not show significant associations with alcohol use that may lead to the child's mental health being unaffected [17]. Therefore, it is crucial to consider both parents when assessing the child's risk of developing substance use disorders. Implementing technology-based interventions and training to screen and support individuals with tobacco, depression, and alcohol use can improve detection and provide protection for patients during medical appointments [18].

Parent-Child Psychopathology Associations

Research indicates that women who have substance use disorders often experience interpersonal trauma and insecure attachment. The presence of a substance use disorder during pregnancy and prenatal stages in mothers is associated with adverse outcomes for neonates, fetuses, and young children. Maternal drug use is also connected to psychiatric comorbidities, dysfunctional parenting styles, emotional detachment, impaired reflective functioning, delayed developmental milestones, and disrupted attachment patterns in children. Even after drug use is discontinued or effectively managed, the psychological and relational dynamics that influence parenting formation can be affected, limiting reflective parental performance and complicating the parent-child bond [19]. Researchers have uncovered that maternal alcohol use disorder (AUD) increases the risk of developing alcohol use disorder (AUD) in daughters more than in sons, whereas paternal AUD elevates the risk of AUD and cannabis use in sons more than in daughters [20]. These findings lend support to the notion that psychopathology is transmitted based on sex, beyond solely AUD. In contrast to adoption research, which revealed a weak association between birth mother personality traits and callous, unemotional behaviors in children, a study on children of twins found no genetic correlation between parental control and child externalizing difficulties [21]. Previous research on children of twins suggests that parents who exhibit inadequate parenting behaviors may have children who are predisposed to psychopathology, indicating that both phenotypes may share the same underlying cause. Ultimately, parental exposure to drug use increases the likelihood of children developing substance use disorders (SUDs) and various mental health issues, potentially initiating an intergenerational cycle of psychopathology [19].

Global Prevalence

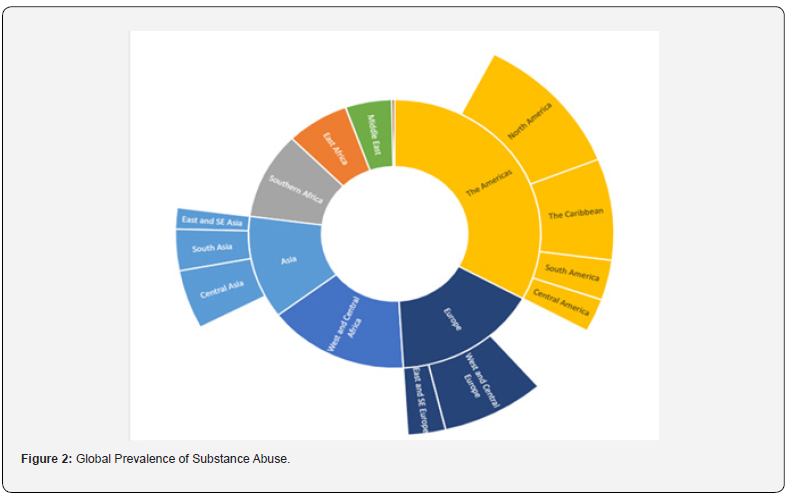
Global estimates suggest that approximately 2.2% of individuals suffer from substance use disorders, with alcohol use disorders being more prevalent at 1.5% compared to other drug use disorders (0.8% overall) [22]. This includes specific drugs such as cannabis, opioids, amphetamines, and cocaine, which have varying degrees of prevalence (e.g, cannabis accounts for 0.32% of substance use disorders, opioids for 0.29%, amphetamines for 0.10%, and cocaine for 0.06%) [22]. The likelihood of using alcohol and drugs increases dramatically in subsequent generations, according to various studies [1,4,6,23-27]. With the exception of intellectual disability, which is more common in low-income nations, substance use disorders have been found to be more widespread in high-income countries [22]. Global Drug Report 2022 from the UN Office on Drugs and Crime (UNODC) estimates that 284 million individuals worldwide between the ages of 15 and 64 took drugs in 2020, a 26% rise from the preceding ten years. Those under 35 make up the bulk of the population in both Africa and Latin America. Adolescent substance use is profoundly influenced by social and environmental factors, such as peer pressure and exposure to substance use [18]. To effectively mitigate teenage substance use, preventive and intervention strategies need to comprehensively consider the significance of these social and environmental elements (Figure 2).
Discussion

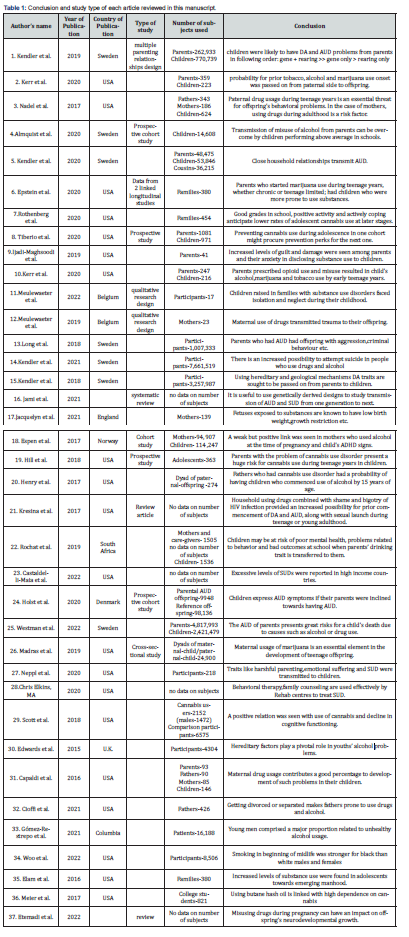
Our review provides a comprehensive examination of the existing body of literature on the genetic underpinnings of parental alcohol and drug use and its associated outcomes in offspring. This topic elicits considerable interest, and the reviewed studies collectively reveal a significant burden of guilt and trauma experienced by parents, coupled with their apprehension regarding the potential disclosure of drug addiction (DA) or alcohol use disorder (AUD) to their children [28]. Previous studies have indicated the genetic liability for AUD and DA has an impact on the likelihood of suicide attempts and death [29]. Moreover, children raised in families affected by drug and alcohol abuse have reported experiences of abandonment and isolation during their childhood, which contributes to their inclination towards social connections involving alcohol use, drug addiction (DA), and recovery [2]. Additionally, there is evidence of genetic overlap across different phenotypes. For instance, parental drug and alcohol use has been found to be associated with various externalizing and internalizing characteristics in their children, such as attention problems, lower academic performance, criminal behavior, and depression [21,23-24]. Studies examining alcohol and substance abuse during pregnancy have indicated that fetuses exposed to marijuana in utero exhibit a significant reduction in D2 gene expression in the amygdala. Furthermore, prenatal cocaine exposure is commonly associated with perinatal effects such as prematurity, growth restriction, and low birth weight [30]. Additionally, although the association is weak, there is evidence of a positive link between maternal alcohol use during pregnancy and the manifestation of ADHD symptoms in offspring [16,31]. Literature findings demonstrate that when drug use is prevalent within the family and household, combined with the presence of shame and discrimination due to HIV infection, there is an increased likelihood of early initiation of drug addiction (DA) and alcohol use disorder (AUD), as well as early engagement in sexual activities during adolescence or young adulthood [32]. Thus, our research suggests that both environmental and genetic mechanisms contribute to the transmission of DA and AUD traits from parents to their offspring. Furthermore, employing genetically informed study designs to investigate intergenerational transmission proves valuable in understanding the impact on children's mental well-being and associated consequences, as well as the process of transmission within families (Table 1).
Future Recommendations

Presently, there is a global escalation in the prevalence of drug and alcohol misuse, resulting in both enduring and immediate ramifications. The etiological factors contributing to this phenomenon vary across nations, cities, and individuals. High-stress environments, peer pressure, inadequate parental care or indifference towards children, and family instability, among other factors, emerge as significant contributors to the development of alcohol use disorder (AUD) and drug addiction (DA) [1]. The key factor contributing to parent-child transmission of substance use is a lack of parental awareness regarding the detrimental consequences of drug and alcohol abuse on their future offspring. A significant proportion of young individuals initiate substance use solely for recreational purposes and to enhance their social status, often unaware of the potential repercussions. The most effective approach to prevent teenage substance use is to foster the development of their social and personal skills. These skills encompass the ability to effectively navigate challenging situations (i.e., emotional regulation), achieve academic success (i.e., cognitive competence), and engage in positive activities such as clubs, sports, and volunteer work [26,33].

The authors recommend the usage of evidence-based interventions such as counseling and therapy which may be employed as effective strategies for addressing addiction. The primary objective of addiction treatment and counseling is to target the underlying issues that contribute to the condition, with the aim of preventing relapse. Behavioral therapy, motivational therapy, and family counseling are widely recognized therapeutic approaches utilized by rehabilitation centers to effectively address substance use disorders [34]. It is imperative to establish drug rehabilitation centers in key urban areas across the country, as these centers serve a dual purpose: providing comprehensive treatment for individuals with substance use disorders and conducting targeted awareness campaigns on drug abuse, particularly in areas with a high prevalence of alcohol use disorder (AUD) and drug addiction (DA).

Limitations

One concern regarding the measurement of parental alcohol abuse is the variation in the duration of the original studies. Only a few studies included in our analysis combined these time periods in their research [6, 23-24]. Another limitation is the small number of participants and the reliance on inpatient care data, which primarily includes severe cases [14,19,23]. One study examined the relationship between parental alcohol use disorder (AUD) registration and the subsequent registration of AUD in their offspring. However, transmission occurred prior to registration, making it an imprecise indicator of the onset of AUD [25]. It is likely, though not certain, that alcohol use during pregnancy is underreported due to the social stigma associated with it [16]. Lifestyle factors such as strong sibling relationships, participation in self-help programs, and individual characteristics including smoking, dietary habits, and exercise were not addressed [15].

The long-term diagnosis of cannabis use disorder (CUD) was not tracked, and the extent of exposure of young individuals to parental cannabis use remains unclear. Grades obtained during adolescence may serve as proxy variables for protective factors (such as dedication to education, avoidance of problematic peers, and strong cognitive functioning) that may reduce cannabis use [35]. Future studies conducted in a legal marijuana setting may reveal patterns that were not apparent when marijuana use was prohibited. The effects of genetic and other neurobiological factors on cannabis use are currently not measured in research, which hampers the exploration of familial influences. Some studies only reflect the general demographics of parents experiencing homelessness [28]. These measurements were taken before the legalization movement and the increase in cannabis potency [36]. It is possible that as recreational cannabis use becomes more prevalent and potent, it may increasingly interfere with parenting [37]. Future research should focus on the generalizability of these results to individuals from diverse demographic and racial/ethnic backgrounds. Additionally, the justifications for initial prescription (e.g., surgery) and the patients' experience of physical discomfort were not evaluated. There was insufficient variation to include long-term or developmentally specific outcomes (e.g., consequences of prescription opioid misuse throughout children's development) and the frequency of prescription opioid misuse and opioid use disorder. The impact of socioeconomic status on the study results remains unclear due to a lack of data on family socioeconomic status [2].

Conclusion

In conclusion, this research aimed to explore the relationship between parental alcohol use disorder (AUD) and drug addiction (DA) and the transmission of traits to offspring. Based on a comprehensive analysis of the literature, it can be concluded that parental drug abuse is associated with various internalizing and externalizing behaviors in children, including attention issues, academic underachievement, criminal behavior, and depression. The risks of developing AUD, drug misuse, and engaging in criminal conduct differ between boys and girls based on maternal and paternal AUD. There appear to be sex-specific components involved in the transmission of psychopathology within the externalizing spectrum. Drug abuse during pregnancy can have significant implications for the mental health of the fetus. Furthermore, researchers have also identified that AUD spreads through a contagious environmental process that occurs within families and is likely facilitated by the exchange of expectations and role models associated with heavy drinking. Further studies are needed to elucidate the critical roles played by both genetic and environmental factors in transmission processes.


To Know more about Academic Journal of Pediatrics & Neonatology
Click here: https://juniperpublishers.com/ajpn/index.php

To Know more about our Juniper Publishers
Click here: https://juniperpublishers.com/index.php


Tuesday, March 26, 2024

Evolution and the Chemistry of Life - Juniper Publishers

 Organic & Medicinal Chemistry - Juniper Publishers

Abstract

In this paper, we show the physics and chemistry of how life may have begun up to the stage of producing three amino acids and sugar. The reaction is telescopic to produce even more proteins. We use the parameters from Astro theology Mathematics covered extensively in other papers by this author.

Keywords: Chromium; Life Chemistry; Amino Acids, Butanoic Acid; Tryptophan; Cystene; L- Glutathione

Introduction

In this brief paper, we develop the balanced chemical equation that shows that life began from three amino acids which produced sugar. We show how Physics, or Astroheology, melds with Chemistry, the Periodic Table.
G/Coulomb= Chromium
6.67/1.602=24=Cr
Mass Cr=55.996 +26e-=1/54=t
t=eM=1/54=3.989≈4=M
24(938)=2.25=9/4=c²/M
24 x938+26(5.1099)=1/4.416=1/148
Ln 148=5.0=E ⇒y=y′ t=3
51.996 x 24=1.2479≈1.25=Emin
t=0.801

2(5.1099)(26=265.7
Butanoic Acid implies L-Tryptophan
C2H4O m mass
44.0262 x 6.023=265.7

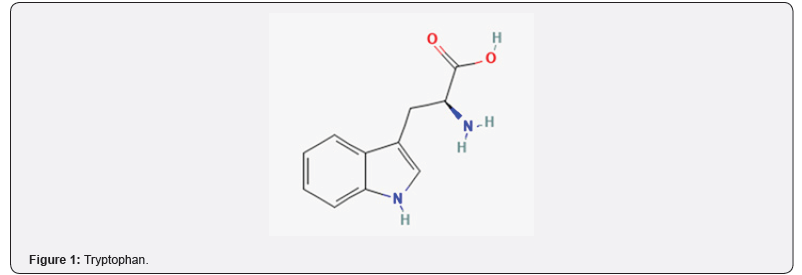
Butanoic acid results from L-Tryptophan. It is a n immune response for Ble Green Algae Cyanobacteria – one of the oldest life forms on Earth. Cyanobacteria forms Vitamin B12 (Figure 1).

NaCl + HOH = Na(OH) + HCl
Zn(OH) + HCl = HOH + ZnCl
HOH = H + OH
2 ZnCl + H2O + C6H12O2 = 2Zn + 2HCl + 3C2H4O
Zinc +Water + Sugar =Zinc Mineral +Stomach Acid+ Butanoic
Acid
2(100.83)+1(18.02)+1(116.16)=2022=H2 acid
C10H12N3O6S + 24 H2O = 10 CO2 + H2SO4 + 3 NO2 + 29 H2
L- glutathione
24 (18.02)+1(302.28)=734.28 -100=265
Ethylene Oxide
C2H4O 44.05(6.023)=265=SF
t=e^M=e^2.65=1.415=sqrt2=E=sin 45+cos 45
For glutathione we need cystine and glutamate.
s=E ×t=|E||t|sinn θ
sin θ =s/[Et]
y=y′ ⇒E=5, t=3
Et=15
s=Et
s=E²Et sin θ
sin θ =s/E²=tan θ =sin θ /cos θ
sinθcos θ =sin θ
cos θ =1
θ =0, π =t
π2 - π -1=57.29°=1 rad=E
3²+x²=15²
x²=225/9
x²=25=E² Perfect Square
t=E

Cyanobacteria leads to Butanoic Acid which leads to Iron and red blood cells and oxygen metabolism. It also leads to Zinc. Butanoic acid also leads to H2 Acid. Cysteine leads to Sulphur.

Try Mo M=204.29
Cys Mol/ M=121.15
SUM325.44 x 6.023=1960 = infinity divergent
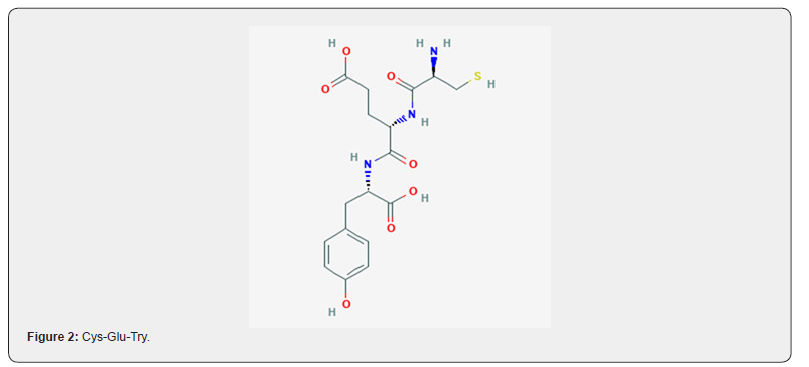
Immunoglobulins evolved from Cys, Try, and Glu (Figure 2)

6 C17H23N307S + 5652 H2O =5613 H2 +17 C6H12O6 + 6 H2SO4 + 1842 NO3 Cys-Glu-Try  Sugar +Volcanos. 413.4 x 6.023=2489=1/402=1/Re 1/Re=VF/IF =1/2rhov^2/[Ma] =1/2(4/Pi)v^2=[4 x 1/sqrt2] V=148.7 M= Ln 148.7=5.00=E

Conclusion

We have shown that life began with a combination of three amino acids (Cys-Glu-Tyr) which produced acid and sugar.


To Know more about Organic & Medicinal Chemistry International Journal
Click here: https://juniperpublishers.com/omcij/index.php

To Know more about our Juniper Publishers
Click here: https://juniperpublishers.com/index.php


Monday, March 25, 2024

Decoding Attentional Task Performance Using Electroencephalogram Signals - Juniper Publishers

 Neurology & Neurosurgery - Juniper Publishers

Abstract

Background: Electroencephalogram patterns help in evaluating the extent of ischemic brain injury and predicting functional performance.

Aim: To determine a possible correlation between attentional task performance and electroencephalogram waves.

Methods: The cerebral activity of 12 healthy young adults was investigated using an electroencephalogram while they underwent the Trail-Making Test-A and B as attentional tasks.

Results: A significant correlation was observed between a stronger occipital delta power during rest and higher error rates, as well as weaker temporal and central delta power during the Trail-Making Test-B and longer task completion times. Delta waves during both the resting-state and task conditions correlated with task performance, which might be affected by the induced cerebral lobes.

Conclusion: The default mode network might predict attention deficits. Our findings further our understanding of the correlation between the default mode network and attentional task performance.

Keywords: Attentional function; Brain function; Brain injury; Electroencephalography; Neuroimaging

Abbreviations: EEG: Electroencephalogram; DMN: Default Mode Network; TMT: Trail-Making Test

Introduction

Implementation of modular assessments of cognitive capabilities at the individual level is crucial in the realm of personalized care and rehabilitation [1]. Rapid transmission of information across the brain underscores the importance of non-invasive neuroimaging techniques, such as electroencephalogram (EEG) indices. These indices exhibit sensitivity to fluctuations in the human brain, reflecting spontaneous brain activity with excellent temporal resolution [2]. Additionally, EEG signals serve as important neuro-electrophysiological indicators of brain activity [3]. Over the past decade, various new EEG systems have emerged, enabling the recording of brain activity during movement [4]. While a single-dimensional measure, such as pupil size, may be suitable when specific data parameters and goals are well defined, multidimensional signals offer a more viable choice. The EEG gathers information on a variety of functions, including attention, memory, and emotions [5]. Accordingly, the EEG elucidates important effects of brain networks on attentional function from the perspective of brain connections and provides potential physiological biomarkers for predicting attention [6]. Resting-state EEG data can delineate inter-individual variability at rest and its correlation with attentional capacity and autistic behavioral patterns [7]. Different EEG patterns reflect various degrees of ischemic brain injury, with some proving reliable predictors of functional performance [8].

Attention is a fundamental component of all the cognitive and perceptual processes [9]. Similar to other networks in the brain, the human attention system is complex. At any moment, attention can shift between the external and internal stimuli [10]. The literature highlights three primary mechanisms: global, local, and self-attention mechanisms [11]. Attention, as a limited cognitive resource, selectively focuses on discrete aspects of information while ignoring others; it is typically divided into two types: active (top-down or endogenous) and passive (bottom-up or exogenous) [12]. An externally directed attentive state often corresponds to reduced focus on internally oriented mental processes [13]. Sufficiently strong attentive states may impair conscious awareness of both the environment and oneself [14]. Previous studies have revealed the functional roles of alpha (α)-band oscillations [15], which are the most prevalent rhythms in EEG recordings and spread through most cortical regions [15]. However, the role of the alpha wave remains debatable [15]. Elevated parietal α power [16] is associated with a shift from attention to the default mode, which suppresses external stimulus processing [17]. This increase is usually accompanied by an increase in frontal theta (θ) power [16], reflecting cognitive control-task execution, memory function, and error processing [17,18]. Greater θ activity is believed to reflect heightened effort in meeting the increasing cognitive demands of prolonged tasks [16]. Furthermore, heightened power in slow-frequency bands (i.e., θ and α) is associated with lower performance [17]. When the functional state of the brain is suppressed, slow waves with frequencies below 8 Hz occur, namely, δ waves and θ waves [19].

This discourse between power band-associated cognitive performance remains unresolved. To develop novel methods for evaluating attentional function, we must further investigate the fundamental brain mechanisms involved in attentional tasks. Therefore, this study aimed to determine a potential correlation between attentional task performance and EEG waves. By delving into the default mode network (DMN), this study not only unveils insights into attentional deficits but also contributes to our comprehension of the DMN's role.

Methods

Participants

Twelve healthy young adults (seven women and five men; age: 21.3 ± 0.62 years) participated in the present study. All prospective participants were provided with a comprehensive explanation of the study’s safety protocols and were assured that their personal identifying information would remain confidential; thereafter, they provided written informed consent for study participation. Additional informed consent was obtained from all participants whose identifiable information was included in the study. None of the participants had a history of major physical disorders, including neurological illnesses, brain injury, or psychiatric illnesses. This study was approved by the Ethics Committee of Nishikyushu University (approval no. 22EAB19) and conformed to the principles of the Declaration of Helsinki and its later amendments.

Task

The Trail-Making Test (TMT) comprises two distinct parts: Part A requires patients to sequentially connect 25 encircled numbers (through lines) dispersed in a pseudo-random manner on a sheet; In TMT Part B, participants alternate between numbers and letters when connecting different items in an ascending order (i.e., 1, A, 2, B, etc.) [20].

Experimental Setup

Participants were seated in a quiet room on a chair with a backrest and placed their forearms in a relaxed position on a table. They were instructed to perform the TMT without any additional movements, such as head movement, and maintain the same posture throughout the experiment. Additionally, participants were instructed to remain silent throughout the experiment, relax without thinking, and fixate their gaze on a cross displayed on a piece of paper in front of them during both task performance and resting periods.

Experimental Protocol

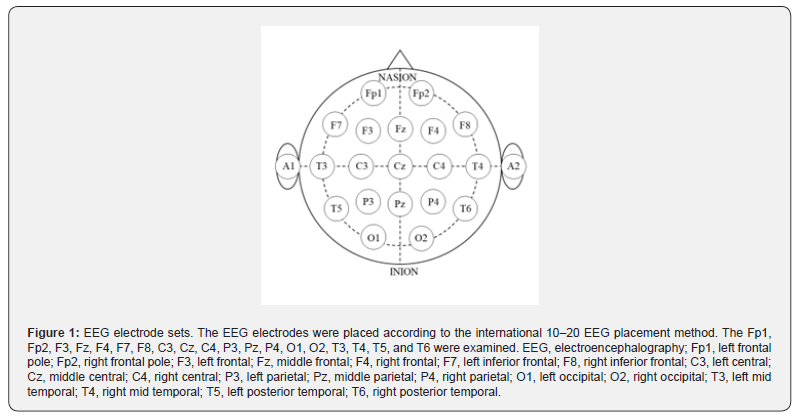
The experimental protocol comprised two tasks, each preceded by a 1-min rest period. EEG measurements were recorded continuously during the experiment using Polymate Pro MP6100 (Miyuki Giken, Tokyo, Japan). The EEG recorded at the scalp level represents the aggregate currents of the electrical fields generated by neural activity in cortical neural circuits [21]. Prior to electrode placement, the skin was prepared with alcohol, and the electrodes were affixed to an elastic cap using a holder. Based on the international 10-20 EEG placement system, 19 gold-coated active EEG electrodes were placed at specific cortical locations: Fp1 (left frontal pole), Fp2 (right frontal pole), F3 (left frontal), Fz (middle frontal), F4 (right frontal), F7 (left inferior frontal), F8 (right inferior frontal), C3 (left central), Cz (middle central), C4 (right central), P3 (left parietal), Pz (middle parietal), P4 (right parietal), O1 (left occipital), O2 (right occipital), T3 (left mid temporal), T4 (right mid temporal), T5 (left posterior temporal), and T6 (right posterior temporal) (Figure 1).

Data Analysis

The EEG data were sampled at a rate of 1,000 Hz and filtered within the 1-60 Hz range using a bandpass filter. Data containing eye blinks or muscle movement artifacts were excluded. Power spectrum analysis was conducting using the Electro Magnetic Source Estimation Data Editor (Cortech Solutions, Wilmington, NC). Six EEG datasets (delta, theta, alpha, beta, low-gamma, and high-gamma) were used for each electrode. Furthermore, waves lying within the 0-4 Hz, 5-8 Hz, 9-13 Hz, 14-30 Hz, 31-50 Hz, and >50 Hz ranges were categorized as delta, theta, alpha, beta, low-gamma, and high-gamma waves, respectively.

Statistical Analysis

The mean power level was calculated for each resting and task condition. Spearman’s rank correlation was used to examine the correlation between task performance and EEG power levels during rest and TMT tasks. Furthermore, IBM SPSS Statistics version 20.0 (IBM Corp., Armonk, NY, USA) was used for statistical analysis. Statistical significance was set at p <0.05.

Results

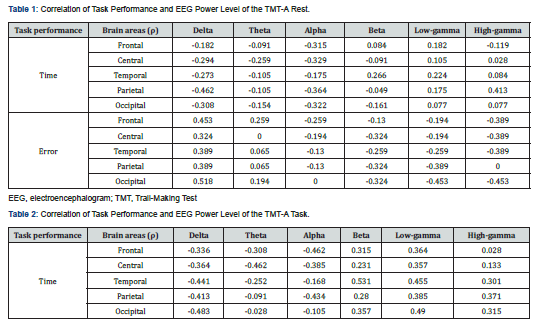
The associations between task performance and EEG power levels during the TMT-A rest and task conditions are summarized in Tables 1 and 2, respectively. Notably, no significant correlations were observed between task performance and EEG power levels for the TMT-A. The correlations between task performance and EEG power levels in the TMT-B rest and task conditions are summarized in Tables 3 and 4. Stronger occipital delta power at rest was significantly correlated with more errors. Additionally, weaker temporal and central delta power during the task were significantly correlated with a longer task time.

Discussion

Recent studies have suggested that attention operates as a rhythmic process, yet the debate continues regarding whether this rhythmicity is influenced by the phase of the ongoing neural oscillations. Addressing this issue requires the use of behavioral tasks that isolate attention from other cognitive functions (perception/decision-making), and the localized monitoring of neural activity with high spatiotemporal resolution across the brain regions associated with the attentional network.22 In the present study, we investigated the relationship between attentional task performance and EEG frequency using the TMT, which is a simple behavioral task that isolates attention from other cognitive functions. The results showed that a stronger occipital delta power during rest was significantly correlated with more errors. Moreover, weaker temporal and central delta power during TMT-B was significantly correlated with a longer task time. No significant correlations were found between task performance and EEG power levels for TMT-A.

Notably, the modulation of behavioral outcomes through EEG frequencies of 3, 6, and 8 Hz (delta, theta, and alpha bands) throughout the frontal region has been reported in studies focusing on quantifying the phase that predicts the high and low attention states [22]. High amplitudes and percentages of delta waves in the frontal lobe for Fz-F3-F4 demonstrates strong stimulation of the limbic system, strong emotions, flurry thoughts, and confusion [23]. Stress, uncertainty, tension, and the release of adrenaline can contribute to heightened arousal and impact cognitive state [24]. The most dominant patterns of change in patients with attention deficit hyperactivity disorder, schizophrenia, and obsessive-compulsive disorder are power increases across lower frequencies (delta, 1-4 Hz and theta, 4-8 Hz) and decreases across higher frequencies (alpha, 8-13 Hz; beta, 13-30 Hz and gamma, 30-50 Hz) [25]. Impairment of visual attention is associated with differences in EEG features, network activation, and involvement of the right frontal eye field [26]. In contrast, our findings showed that frontal delta power was not correlated with task performance, while stronger occipital delta power during rest was significantly correlated with more errors, and weaker temporal and central delta power during TMT-B was significantly correlated with a longer task time. These results indicate that the influence of delta waves on task performance may be mediated by their interaction with the cerebral lobes, highlighting their role in task specificity. Moreover, these phenomena affect the task performance’s specificity. Furthermore, attentional deficits may be reflected differentially by resting-state and attentional-state EEG data, implying that the DMN may predict attentional deficits.

Additionally, a correlation exists between different EEG frequencies and attentional task performance. A higher theta-beta ratio reflects challenges in attention allocation for a given task [27]. Gamma band activity plays a vital role in many sensory and cognitive processes. Therefore, the peak frequency in the gamma range has received considerable attention [28]. Gamma band activity, combined with frontal midline theta rhythm in the left and right frontal forehead regions, appears to reflect prefrontal function in working memory tasks [29]. Furthermore, lateralized patterns of band phase coupling between the frontal and parietal-occipital regions have been identified during covert visuospatial attention tasks in healthy young adults [30]. While these findings enrich our understanding of the brain mechanisms underlying attention, further exploration into additional EEG frequency considerations and their potential impact on task performance, particularly lateralized patterns, is essential.

This study had some limitations. It focused solely on healthy young adults; therefore, it is unclear whether our results can be generalized to older patients or those with neurological disabilities. Furthermore, the attentional task only utilized the TMT; therefore, whether brain waves during other attentional tasks are comparable to those observed during the TMT remains unclear. Additionally, our study included only a small number of participants. To address these limitations, future studies should include more participants performing tasks under various conditions and investigate brainwave activity across diverse attentional tasks. Despite these limitations, these study findings indicate that stronger occipital delta power during rest is correlated with errors, and weaker temporal and central delta power during tasks is linked to a longer task times, offering insights into the role of brain rhythms in attentional deficits and contributing to our understanding of cognitive functions and neural connections.

Conclusion

Our study identified significant correlations between EEG power levels and attentional task performance. Specifically, stronger occipital delta power during rest was significantly correlated with increased errors, while weaker temporal and central delta power during TMT-B was significantly associated with a longer task time. Delta waves during both the resting-state and task conditions were correlated with task performance, which may also be affected by the induced cerebral lobes. Moreover, our findings suggest the potential predictive value of the DMN for attention deficits. Our findings expand the understanding of the interplay between DMN and attentional task performance, emphasizing the need for further investigations into the intricate relationships between EEG frequencies and attentional task performance.


To Know more about our Juniper Publishers

Friday, March 22, 2024

Digital Angioleiomyoma: A Case Report - Juniper Publishers

 Journal of Case Studies - Juniper Publishers


Abstract

The objective of the article is to raise the index of clinical suspicion of these small, solitary, slow growing, and usually painful benign tumours amongst healthcare professionals who manage foot and ankle pathology. Thus, aiding their inclusion in the differential diagnoses of soft tissue tumours, along with ganglion cyst, giant cell tumour, schwannoma and bursa. The author recounts a case of digital angioleiomyoma and outlines typical signs, symptoms, imaging and histopathological findings. Definitive diagnosis is via histopathology after in toto excision. Recurrence after excision is rare.

Keywords: Angioleiomyoma; Digital angioleiomyoma; Tumour; Foot

Abbreviations: mm: Millimeters; cm: Centimeters; MRI: Magnetic Resonance Imaging; PIPJ: Proximal Interphalangeal Joint

Introduction

Leiomyoma are slow growing benign neoplasms of smooth muscle. They are characterised by the smooth muscle of origin [1,2]. Superficial, e.g. piloleiomyoma arise from the smooth muscle of erector pili muscles in skin. Genitoleiomyoma from vulvar, scrotal or areolar smooth muscle and Vascular or angioleiomyoma originating from vascular smooth muscle of the tunica media of small veins [1-4].

Angioleiomyoma are common throughout the body. Accounting for 5% of all benign soft tissue neoplasms, with 89% of cases present in the extremities. Of which, 66-71% occur in the lower extremity and 22-29% in the upper extremity [5,6], They represent 0.2% of cases of soft tissue tumours occurring in the foot, with the heel being the most common location [2,7]. However, digital angioleiomyoma are rarer accounting for only 9% of pedal cases, with less than 20 cases previously described [2,6,8].

Although cases affecting patients between 12 and 80 years of age appear in the literature, around two thirds of cases occur between the 4th and 6th decades [2,6,8].

Angioleiomyoma affect males to females at a ratio of 1:1.7. A tenfold increased incidence in east Africans compared to Caucasians living in the same temperate climate is noted [9]. However, no direct genetic associations for the development of angioleiomyoma exist [10].

Postulation on the pathogenesis of angioleiomyoma has included minor trauma, hormonal changes in pregnancy; particularly altered oestrogen levels, infection, arteriovenous malformation, venous stasis and traumatic venous congestion [10,11].

Masses are small, typically less than 2 centimetres in diameter, well-defined, often encapsulated, solitary ovoid lesions with glistening yellow, pink, grey, white, silver and brown colouration separately described [2,5,6,10,12].

Four histopathological sub types exist. All are composed of varying concentrations of bundles of eosinophilic smooth muscle cells with cigar or spindle shaped nuclei that stain positively for smooth muscle actin. These surround vascular channels of varying sizes. They exhibit moderately low overall mitotic activity and cellularity with no evidence of atypia [2,5,10,11,13,14]. Reports of intra tumour calcification, mature fat cells, hyalinisation, myxoid changes, organising thrombus and lymphocytic infiltration exist [10,11,14]. Cytology findings following fine needle aspiration show uniform spindle cells mixed with smooth muscle, collagen, macrophages and fat cells. These findings are insufficient to make a diagnosis [11].

Clinically, angioleiomyoma present as solitary, firm, small (<2cm), slow growing and long standing, mobile, sub cutaneous nodules [8,11,14]. Postulated to be due to mass effect, secondary to ischaemic change following contraction of smooth muscle and local nerve compression, pain is a symptom in around two thirds of cases. Exposure to cold and pressure including shoe gear can also elicit symptoms. [2,5,8,11,13,16]. Increasing size with physical activity is possible [8,11,14]. The slow growing nature of the tumours is highlighted by a delay of 4-10 years between subjective onset and excision [2,8].

The vast majority of authors recommend that excision with histopathology is the standard of care for diagnosis and exclusion of malignancy [8,10,11,14,16]. Excision has a good prognosis with low recurrence rates around 1:250 [5]. If recurrence occurs, repeat examination of the original histopathology to rule out leiomyosarcoma should be undertaken [10]. Malignant change is rare with only a few cases of leiomyosarcoma reported in the literature [1].

4.1. Imaging

Aside from increased soft tissue intensity at the site of the tumour, plain radiographs are usually unremarkable [14]. In some cases, secondary compression phenomenon of bone of the intermediate phalanx of a lower limb digital mass can appreciated on X –ray [8]. Ultrasound examination shows; well defined, ovoid, homogenous, non-compressible mass. Descriptions of anechoic and hypoechoic areas alternating with isoechoic regions are found in the literature. Feeding arteries may be visualised as tubular structures with numerous intra lesion branches [11,17,18].

Magnetic resonance imaging (MRI) changes are consistently reported and secondary to varied proportions of component smooth muscle cells and blood vessels. T1 images typically show well-circumscribed homogenous masses, which are isointense to skeletal muscle. A thin hypointense capsule surrounding the lesion are often present on both T1 and T2 images [11,12,14]. Within the tumour heterogeneous, hyper and isointense areas are visible on T2 and STIR images. Hyperintense areas correspond to smooth muscle and are multiple linear or branching in appearance. These areas show strong enhancement on intra venous contrast. Areas of tough fibrous tissue or intravascular thrombi correspond to isointense areas. These do not show enhancement on contrast [11,12,14]. MRI cannot differentiate histopathological sub types [11,12].

Case Report

A 62-year-old male patient presented in clinic describing a 3-year worsening history of pain and soreness from a slow growing mass affecting the dorsal aspect of his left third toe. The mass had been present for five years prior to his discomfort. Symptoms were worse with walking and wearing safety footwear. Relief achieved from removing footwear. The patient subjectively scored the pain at 8/10 on visual analogue scale when wearing safety shoes for work. No subjective colour change or swelling noted, he had noticed gradual enlargement of the mass. No direct trauma history recalled. The pain caused him to limp and utilise oral analgesia. An occasional tingling pain in the digit could cause sleep disturbance. Embarrassed by the appearance of the mass, the patient had avoided taking his grandchildren swimming. No previous treatment or imaging had taken place. When questioned, the patient’s idea was that the mass was a ganglion; his main concerns were the discomfort as well as the appearance. His expectation was to achieve a reduction of symptoms. He felt that this warranted an operation.

Medical history was remarkable for hypertension, asthma and a history of hepatitis A. Previous surgery: laparoscopic cholecystectomy and left lateral ankle ganglion excision.

Medication: Salbutamol, Beclometasone with formoterol inhaler and Ramipril 2.5mg.

No known allergies.

On examination, vascular and neurological supply to the distal lower limb was intact. Skin was of normal colour, temperature and texture. Patient was using a well-fitting running shoe.

Musculoskeletal examination was grossly normal. At the level of the proximal interphalangeal joint (pipj) of the left third toe, a well-defined, ovoid, rubber, partially fluctuant, non-emptying, non-tender, non-pulsatile soft tissue mass was present. Differential diagnoses included, ganglion cyst and giant cell tumour of tendon sheath. Management options discussed, included do nothing, needle biopsy and in toto excision with histopathology. He considered these whilst waiting for the results of plain radiographs and ultrasound examination.

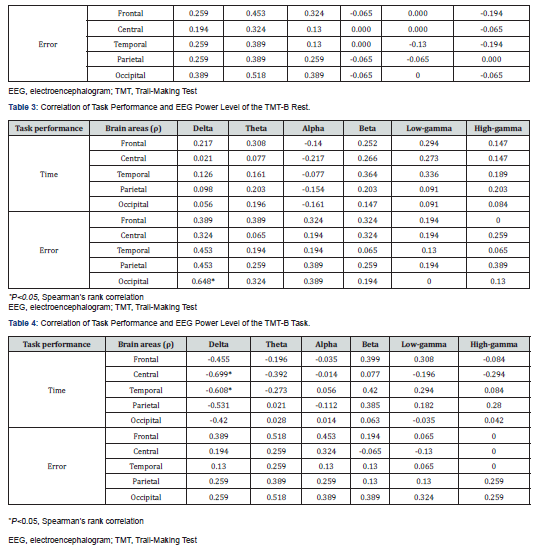
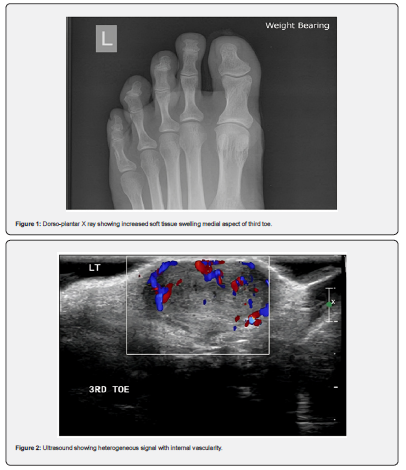
Dorso-plantar radiograph (Figure 1) highlighted mild increased soft tissue swelling on the medial aspect of the left third toe at the level of the proximal interphalangeal joint. Ultrasound (Figure 2) revealed, a large, 1.9cm x 1.3cm lesion showing internal vascularity overlying the dorsal aspect of the proximal interphalangeal joint of the left third toe. Magnetic resonance imaging (MRI) was advised for further characterisation.

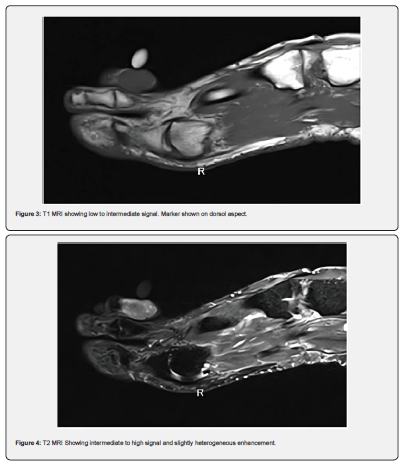
Measuring 0.9 x 1.1 by 1.8 cm a soft tissue mass at the level of the left third pipj could be visualised on MRI. This gave low to Intermediate signal on T1 (Figure 3), intermediate to high on T2 STIR imaging with slightly heterogeneous enhancement. (Figure 4) Bone marrow was normal on all sequences. Radiology reported, “Appearances are nonspecific and could represent a giant cell tumour of the tendon sheath or other benign pathology.”

The patient elected for excision with histopathology. Under regional ankle anaesthesia with ankle tourniquet and standard skin preparation and draping. A longitudinal double elliptical skin incision centred over the mass was performed. Blunt dissection revealed a silver/white well-demarcated mass surrounded by a thin, weakly adhered capsule. No vascular or neurological structures supplied the mass. Following in toto excision, a non-absorbable suture placed at the cephalic end of the mass aided orientation for histopathology. Inspection of the structures adjacent and deep to the mass found them normal and healthy. Skin closure with simple interrupted 3-0 sutures followed copious saline irrigation. Post-operative progress was uneventful, and sutures removed after two weeks with return to normal footwear and work. Follow up two months later was unremarkable with the patient pain free. He had returned to swimming.

Results and Discussion

Histopathology described the samples macroscopic findings as “single lobular greyish brown soft tissue measuring 18mm x 13mm x 10 mm” and microscopically “an angioleiomyoma that is seen reaching the excision margin focally. No malignancy is present.” Concluding, “Lesion left third toe: Angioleiomyoma.”

Whilst relatively common in the lower extremity and the foot, the rarer, digital location in this instance is worthy of reporting. The long-standing, slow growing nature of the lesion combined with worsening pain experienced by the patient are consistent with descriptions in the literature. Imaging is unable to confer definitive diagnosis. However, the findings in this case, particularly MRI are also in keeping with previous descriptions. Definitive diagnosis achieved via histopathology and recurrence is rare after excision.

Clinicians should consider Angioleiomyoma in the differential diagnoses of solitary soft tissue masses within the foot. Particularly when, long-standing and slow growing tumours are accompanied by characteristic mixed hyper and iso intense areas on T2 MRI. 


Thursday, March 21, 2024

Complications In Gallbladder Surgery: Laparotomy Vs. Laparoscopy, A Comparative Review - Juniper Publishers

 Journal of Surgery- Juniper Publishers


Abstract

Gallbladder disease is a condition that affects nearly 20% of adults in the United States. Roughly 20% of them will develop symptoms throughout their lives; the risk of cholecystitis increases with age and sex, being females in a higher-risk population with a female-to-male ratio of 4:1. An early cholecystectomy is the best choice to treat gallbladder disease. However, it is imperative to determine the best surgical approach based on the risks and benefits for the patient. This comparative review addresses the clinical relevance of gallbladder surgery by examining the diverse indications considering factors such as the severity of the condition, patient preferences, and surgeon experience. The choice between procedures has significant implications for patient outcomes, recovery time, healthcare costs, and sustainability. Robust evidence supports laparoscopic cholecystectomy due to its efficacy and lower risk for the patient. The purpose of this article is to review the current and most relevant concepts in comparing laparoscopic versus open gallbladder surgery, its indications, technique, and complications.

Keywords: Bladder Surgery; Cholecystectomy; Laparoscopy; Laparotomy; Minimally Invasive Surgery

Abbreviations: GD: Gallbladder disease; GB: Gallbladder; GS: Gallstones; CBD: Common bile duct; CT: Computed Tomography; MRI: Magnetic Resonance Imaging; LFTs: Liver function tests; LC: Laparoscopic cholecystectomy; OS: Open surgery; AC: Acute cholecystitis; ECC: Early cholecystectomy; SIS: Surgical Indications for Surgery; PVS: Percutaneous or endoscopic gallbladder drainage; SSI: Surgical Site Infection; IV: Intravenous; PCS: Postcholecystectomy syndrome; CO: Carbon monoxide; PG: Patient group; TE: Technical factors; WR: Wound-related complications; BI: Bile duct injury; RCBDS: Retained common bile duct stones; PH: Postoperative pain; RH: Respiratory complications; TRH: Trocar site hernias; ER: Early recovery; HS: Hospital stay

Introduction

Gallbladder disease encompasses a range of disorders affecting the gallbladder, including gallstones, cholecystitis, and biliary dyskinesia. It has a higher incidence in specific populations, particularly individuals over 40, women, and those with obesity. Clinical features include severe abdominal pain, nausea, vomiting, and jaundice. The diagnosis typically involves imaging studies such as ultrasound, CT scans, MRI, and liver function tests. Treatment options depend on the specific condition and can range from lifestyle modifications and medications to surgical interventions, with cholecystectomy being the most common and practical approach to managing gallbladder disease. Early diagnosis and appropriate treatment are crucial to prevent complications and improve patients’ quality of life [1,2]. Gallbladder surgery, or cholecystectomy, is a standard surgical procedure to treat various gallbladder-related disorders. This review article delves into the indications for gallbladder surgery and offers an in-depth analysis of the two primary surgical approaches, laparotomy and laparoscopy. We aim to comprehensively understand the clinical considerations when deciding between these surgical methods [2,3]. With an increasing number of gallbladder surgeries performed annually worldwide, there is a growing demand for a comprehensive evaluation of the indications and surgical techniques employed [4,5].

This comparative review addresses the clinical relevance of gallbladder surgery by examining the diverse indications considering factors such as the severity of the condition, patient preferences, and surgeon experience. The choice between laparotomy and laparoscopy (minimally invasive surgery) has significant implications for patient outcomes, recovery time, and healthcare costs. Thus, understanding these surgical approaches’ merits and drawbacks is pivotal for patients and healthcare providers [6]. This review will discuss the specific indications for gallbladder surgery, encompassing acute and chronic gallbladder diseases. Additionally, we will present a detailed comparison of the laparotomy and laparoscopy techniques, including their respective procedural aspects, advantages, and limitations. By synthesizing current evidence and clinical insights, this article offers guidance for optimizing patient care and surgical decisionmaking in the context of gallbladder surgery.

Gallbladder Surgery by Laparotomy

Procedure and Technique

Surgical and Endoscopic Approaches for Gallstone Diseases

When managing gallstone diseases, various surgical and endoscopic procedures are available. Laparotomy is a conventional surgical technique used to treat these diseases, involving an abdominal incision to access the gallbladder and address gallstone-related complications [7,8]. On the other hand, for cholelithiasis complicated by choledocholithiasis (the presence of stones in the bile duct), the choice between one-session and two-session treatments depends on multiple factors. One-session treatment, often performed endoscopically, offers benefits such as shorter hospital stays and cost-effectiveness [9]. This minimally invasive endoscopic approach involves the insertion of specialized instruments and a camera through small incisions to visualize, diagnose, and remove gallstones from the bile duct.

Timing of Cholecystectomy in Acute Cholecystitis

Acute cholecystitis commonly results from gallstone blockage in the cystic duct and primarily necessitates cholecystectomy as the standard treatment [7]. The debate revolves around the timing of this surgical procedure. Early laparoscopic cholecystectomy is increasingly favored over delayed cholecystectomy due to several advantages. It offers a higher quality of life, reduced morbidity rates, and cost savings within the hospital [9]. This technique entails making small incisions in the abdomen and inserting a laparoscope, allowing the surgeon to view and remove the gallbladder. The choice of timing, whether early or delayed, should be personalized, considering the patient’s clinical condition and the available hospital resources [9].

Management of Acute Cholecystitis

Acute cholecystitis is a severe condition associated with gallstones, with an approximate 3% mortality rate that escalates with patient age and comorbidities [7]. The gold standard for treating acute cholecystitis is early laparoscopic cholecystectomy, accompanied by the appropriate administration of fluids, electrolytes, and antibiotics [8]. However, alternative techniques like gallbladder drainage are considered for patients with high operational risks. This drainage can be accomplished through percutaneous or endoscopic methods and has demonstrated clinical success in most cases [9]. These approaches use specialized instruments to access the gallbladder or bile ducts through minimally invasive means. After recovery from acute cholecystitis, patients who have undergone drainage may contemplate cholecystectomy as a definitive treatment. Nonetheless, in elderly patients or those with significant comorbidities, the risks associated with cholecystectomy may still be high, making alternative techniques such as gallstone removal through a percutaneous tract or endoscopy more appropriate [9].

Complications of Open Cholecystectomy

Open cholecystectomy is performed when the laparoscopic critical view of safety cannot be achieved for suspected or confirmed gallbladder malignancy or patient clinical condition prohibiting a laparoscopic approach. The complication rates associated with open cholecystectomy are higher than a laparoscopic cholecystectomy [10]. The incisional site required for an open cholecystectomy is more significant than in laparoscopic surgery, resulting in a higher incidence of incisional hernia formation, adhesion formation, wound infection, hematoma, and postoperative pain [11,12].

i. Hernia formation: Incisional hernia formation is a relatively common complication of abdominal surgery, ranging from 2-20%, and is likely multifactorial and dependent on patient and technical factors [13]. Risk factors include wound infection, connective tissue disorders, and surgical technique [14,15]. Incisional hernias are more common in open abdominal surgery than in minimally invasive surgical techniques [16,19,27]. Open cholecystectomy is associated with a higher risk of Incisional hernia than laparoscopic cholecystectomy [11,17,28]. However, single-incision laparoscopic cholecystectomy is associated with a higher prevalence (4.5%) of Hernia formation compared to open (1.5%) [18,29].

ii. Adhesions: Postoperative adhesion formation is a common complication of intra-abdominal surgeries with a prevalence of over 50% [19]. Adhesion formation involves a complex immune response of cytokines, cellular growth factors, cellular adhesion molecules, neuropeptides, and other growth factors released around the surgical trauma site and are influenced by surgical technique [20]. Open cholecystectomy results in more tissue trauma and an increased inflammatory reaction [21,26]. Laparoscopic cholecystectomy results in less abdominal tissue trauma than open and is associated with less inflammatory reaction and less adhesion formation than open cholecystectomy [20,23].

iii. Postoperative Pain: The traditional incision used for an open cholecystectomy is a right subcostal or Kocher incision. This incision is made 2 centimeters below the right costal margin and extends from the midline laterally to the desired length, usually across the rectus muscle [13]. A complication of the Kocher incision, commonly used in open cholecystectomy, is the development of chronic postoperative pain and paresthesia inferior to the scar, typically due to the division of the ninth intercostal nerve [14,15,24].

iv. Surgical Site Infection: Surgical Site infections (SSI) are the most common healthcare-associated infections [16]. SSIs depend on patient and technical factors such as surgical approach [25]. Open cholecystectomy has been consistently associated with a higher risk of SSI compared to laparoscopic [18-20].

Gallbladder Surgery by Laparoscopy

Procedure and Technique

Laparoscopic cholecystectomy is an innovative and minimally invasive surgical technique designed to address gallbladderrelated ailments effectively. This procedure finds its application in the treatment of a spectrum of conditions, including cholecystitis (both acute and chronic), symptomatic cholelithiasis, biliary dyskinesia, acalculous cholecystitis, gallstone pancreatitis, and gallbladder masses or polyps [30]. To execute this intricate procedure, a specialized set of equipment is meticulously employed, comprising two laparoscopic monitors, a laparoscope equipped with a camera cord and light source, a carbon dioxide source with tubing for insufflation, trocars ranging from 5 mm to 12 mm, an assortment of laparoscopic instruments (such as atraumatic graspers, Maryland graspers, clip applier, electrocautery, and a retrieval bag), a scalpel with an 11/15 blade, forceps, needle driver, and absorbable sutures [22-29].

The laparoscopic cholecystectomy unfolds following anesthesia induction and intubation. It commences with the insufflation of the abdominal cavity to 15 mmHg, employing carbon dioxide. Subsequently, four small incisions are made at strategic points in the abdomen for trocar placement: one above the umbilicus, one below the xiphoid process, and two along the right subcostal region. Utilizing a laparoscope and specialized long instruments, the gallbladder is gently retracted over the liver, allowing for clear visualization of the hepatocystic triangle. The procedure requires meticulous dissection to achieve the critical view of safety, defined by three key criteria: the clearance of fibrous and fatty tissue from the hepatocystic triangle, the presence of only two tubular structures entering the base of the gallbladder, and the separation of the lower third of the gallbladder from the liver to visualize the cystic plate. Once this view is satisfactorily attained, the surgeon can confidently isolate the cystic duct and cystic artery, carefully clipping and transecting both structures. The gallbladder is then meticulously separated from the liver bed using electrocautery or a harmonic scalpel. Hemostasis is ensured after reducing the abdominal insufflation pressure to 8 mmHg for 2 minutes. The extracted gallbladder is placed in a specimen pouch and removed from the abdomen, and all trocars are extracted under direct visualization [30].

The benefits of laparoscopic cholecystectomy are numerous and significant. Patients who undergo this procedure experience less pain, a reduced risk of complications, and a swiffer recovery, enabling a quicker return to their regular activities. Furthermore, the incisions are smaller, resulting in less noticeable wounds and scars. In addition, blood loss during surgery is notably lower compared to traditional methods, and hospital stays tend to be shorter, providing patients with a more efficient and less disruptive recovery process [31,32].

Complications

Laparoscopic cholecystectomy, a minimally invasive surgical procedure to remove the gallbladder, is generally considered a safe and effective treatment for gallbladder-related conditions. However, complications can still arise, including wound infection, bleeding, bile duct injury, retained common bile duct stones, and postcholecystectomy syndrome (PCS) [33]. Wound infection is one of the most common early complications following laparoscopic cholecystectomy. This complication typically manifests as pain, redness, and discharge at the incision sites, posing discomfort to the patient. The risk of infection is often mitigated through strict adherence to aseptic techniques and careful wound care postsurgery [33,34].

Bleeding can occur during the procedure or afterward, leading to the formation of hematomas or collections of blood at the surgical sites. Although bleeding complications are relatively rare, they can delay wound healing and cause discomfort. Close monitoring and prompt management are essential to address this issue [35]. One of the more severe complications is bile duct injury, which may occur during the gallbladder dissection from the liver. Injury to the common bile duct or its branches can lead to bile leakage, scarring, or stricture formation, resulting in symptoms such as jaundice, abdominal pain, or cholangitis. Repairing such injuries often necessitates specialized surgical interventions [35]. Another potential complication is the retention of common bile duct stones, which may inadvertently remain in the bile duct after gallbladder removal. These retained stones can cause recurrent symptoms, including pain, jaundice, or infection. They may require endoscopic procedures or further surgery for removal [33,36].

Post-cholecystectomy syndrome (PCS) is a long-term complication characterized by gastrointestinal symptoms, including abdominal pain, bloating, diarrhea, and dyspepsia. It can persist or develop following gallbladder removal, and its exact etiology is not entirely understood. Management may involve dietary modifications, medications, or further evaluation to rule out other gastrointestinal disorders [33,37].

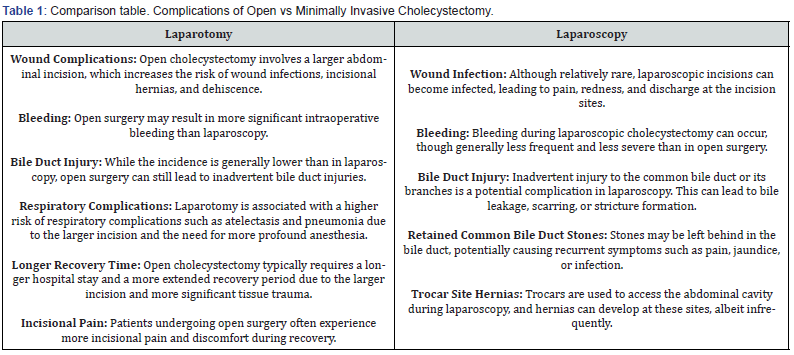
It is important to emphasize that while complications associated with laparoscopic cholecystectomy can occur, the overall incidence remains relatively low. The risk of these complications varies based on factors such as patient characteristics, surgical technique, and the surgical team’s experience. Clinicians must maintain vigilance in recognizing and managing these complications when they do occur to ensure optimal patient outcomes (Table 1).

It is important to note that laparoscopic cholecystectomy is generally associated with fewer complications, a shorter hospital stay, and faster recovery than open surgery. The choice between these approaches is often based on the patient’s medical condition, surgeon’s expertise, and other factors. The risk of complications can also vary depending on the patient’s health status and the complexity of the surgery [38-40].

Conclusion

Gallbladder disease encompasses various disorders, predominantly affecting those over 40, women, and individuals with obesity. Diagnosis involves imaging and liver function tests. Treatment options range from lifestyle changes to cholecystectomy. This article discusses laparotomy and endoscopic approaches, emphasizing the advantages of endoscopy, particularly for complex cases. It promotes early laparoscopic cholecystectomy in acute cholecystitis and underscores personalized care. It outlines the benefits of laparoscopic cholecystectomy, including shorter hospital stays and quicker recovery. This article recognizes the higher complication rates associated with open cholecystectomy and elaborates on complications such as incisional hernias, adhesions, postoperative pain, and surgical site infections. It acknowledges the relevance of alternative techniques. Complications following laparoscopic cholecystectomy, including wound infections, bleeding, bile duct injuries, and postcholecystectomy syndrome, are emphasized, highlighting the importance of prompt recognition and management for favorable patient outcomes. Lastly, the article underscores the significance of personalized care and surgical technique selection for gallstone diseases. It emphasizes the benefits of minimally invasive laparoscopic cholecystectomy and the importance of recognizing and managing complications for positive patient outcomes.

To Know more about Open Access Journal of Surgery

To Know more about our Juniper Publishers

Wednesday, March 20, 2024

Role of Instant Messaging Forensic Investigations on Detection of Corporate Fraud among Commercial Banks in Kenya - Juniper Publishers

 Forensic Sciences & Criminal Investigation - Juniper Publishers


Abstract

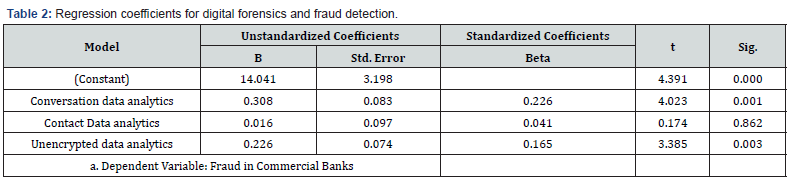
Despite ongoing efforts to curb corporate fraud in both the public and private sectors, the prevalence of such fraudulent activity persists. Notably, digital forensics remains a primary focus of research, given its potential for facilitating fraud detection. In light of this, the study investigates the role of instant messaging forensics, specifically conversation data analytics, contact data analytics and unencrypted data analytics, in detecting corporate fraud within the Kenyan banking industry, guided by Locard’s Exchange Principal Theory. The research adopted a descriptive study design, which incorporated responses from a target population of 380 individuals, primarily from 43 banks and the banking fraud investigation department of the central bank. Our sample size encompassed 114 participants, out of which 100 provided responses through questionnaires and semi-structured instruments. The results indicate that that conversation data analytics (β= 0.308, p =0.001) and unencrypted data analytics (β= 0.226, p =0.003) have a significant positive impact on fraud detection in banks while contact data analytics (β= 0.016, p= 0.862) was found to have a non-significant effect on fraud detection. We recommend the that banks prioritize the adoption of conversation data analytics and unencrypted data analytics as a way to increase fraud detection in their systems.

Keywords: Digital forensics; Conversation data analytics; Contact Data analytics; Unencrypted data analytics; Fraud detection.

Introduction

The accelerating pace of technological and commercial advancements has coincided with a troubling surge in corporate fraud, posing significant challenges to the global financial sector and, specifically, the banking industry. High-profile surveys by leading consultancies and institutions such as the Association of Certified Fraud Examiners (ACFE), PricewaterhouseCoopers, Deloitte, KPMG, and Ernst & Young have underlined this escalating trend, capturing the attention and concern of businesses worldwide. The adverse implications of these fraudulent activities extend beyond destabilizing the banking sector; they also erode profitability, a concern that is especially pronounced in developing economies.

Across both developed and emerging markets, banks grapple with a spectrum of fraudulent activities that range from asset misappropriation to cybercrime, corruption, procurement fraud, and accounting inconsistencies [1]. These activities have been estimated to siphon off between 2% and 7% of banks’ annual revenue, translating to losses in the trillions of dollars on a global scale. This alarming trend necessitates deeper exploration, especially in the context of developing countries where existing research remains scant, Kassem (2014).

In an effort to fortify their defenses against this scourge of corporate fraud, banks globally have escalated their investments in strengthening internal controls and enhancing digital forensics investigation capabilities. The domain of Digital Forensic Investigation (DFI) has emerged as a linchpin in tackling digital crimes, encompassing a gamut of activities from the identification and preservation to the analysis, documentation, and presentation of digital evidence. As digital media increasingly becomes the de facto medium for storing and transmitting information, the significance of specialized forensic techniques in the fight against fraud amplifies, especially in developing countries where fraudulent activities are burgeoning [2]. This study pivots around the Kenyan banking sector, seeking to appraise the impact of instant messaging forensics investigations in detecting fraud. By scrutinizing various branches of instant messaging digital forensics, ranging from conversation data forensics, contact data analytics and unencrypted data forensics, this research aspires to elucidate the role these techniques play in mitigating corporate fraud within banks. The insights gleaned from this study will contribute to the formulation of more efficacious fraud detection and prevention strategies, thereby enhancing financial stability and preserving the profitability of banks.

Literature Review

Theoretical framework

The Locard Exchange Principle (LEP), established by Edmond Locard (1877–1966), the founder of the Lyons Police Technical Laboratory in France, serves as the foundational theory for this study. LEP asserts that every interaction or contact between two entities results in an exchange of trace evidence [3]. This principle has been extended to digital crime investigations, where digital evidence, such as logs or malware, may be present even in the absence of physical contact between the perpetrator and the crime scene [4]. LEP provides a robust theoretical basis for the study’s objectives, as it suggests that traces of digital evidence can be found and analyzed in various forms of digital forensic investigations. LEP posits that digital evidence, such as messages exchanged between fraudsters, can be uncovered through instant messaging forensic investigations, leading to the identification of perpetrators and their criminal activities [5]. The theory also implies that traces of digital evidence may be present on social media platforms used by fraudsters, allowing for the identification and analysis of criminal activities through social media forensic investigations [6]. LEP supports the idea that computer systems and networks can contain digital evidence, such as malware or logs, which can be analyzed through computer forensic investigations to detect and deter corporate fraud [4]. In addition, the theory suggests that mobile devices, which have become indispensable tools for fraudsters, may contain retrievable digital evidence that can be analyzed through mobile forensic investigations to identify and counter corporate fraud [5]. Locard Exchange Principle serves as a valuable theoretical underpinning for this study, emphasizing the significance of digital evidence in combating corporate fraud. By applying LEP to the context of digital forensic investigations in the Kenyan banking industry, this study aimed to contribute to a deeper understanding of the roles played by various forensic methods in detecting and preventing corporate fraud.

Literature review

Instant messaging forensics and fraud detection in banks: Instant messaging, a form of real-time communication enabling private conversations via the internet, has gained significant popularity since its inception in 1996 with the launch of the ‘I Seek You’ service. The evolution of instant messaging has extended beyond text-based conversations to include the exchange of various media formats, location sharing, and voice and video calls. This widespread adoption has led to the incorporation of instant messaging in businesses, organizations, and government agencies worldwide, exemplified by services such as WhatsApp Business Chat and Twitter accounts of government officials. Given the ubiquity of instant messaging, it is crucial for forensic investigators to analyze conversation artifacts during device examinations. Décary-Hétu and Aldridge [4] highlighted the importance of instant messaging forensics in digital crime investigations, but their study did not specifically address its role in various industries such as banking. Previous research on instant messaging forensics has primarily focused on popular applications for Android and iOS mobile operating systems. Studies by Gao and Zhang (2013) and Ovens and Morison (2016) have explored artifacts left by applications such as WeChat and Kik on iOS devices. However, these studies largely centered on the first generation of instant messaging apps, neglecting the latest generation of platforms like WhatsApp and Telegram. While Sgaras et al. (2015) conducted a forensic acquisition and analysis of WhatsApp, Viber, Skype, and Tango on both Android and iOS, their focus was on evidence acquisition in digital forensic investigations rather than evidence assessment and examination processes. Stirparo (2016) examined general iOS forensics information and investigated the security features of Telegram, Signal, and WhatsApp, corroborating Sgaras et al.’s (2015) findings on WhatsApp’s unencrypted Chat Storage SQLite database on iOS. Rathi et al. (2018) analyzed forensic artifacts left by WeChat, Telegram, Viber, and WhatsApp on Android smartphones, revealing methods for retrieving encrypted databases and decrypting them. However, these studies do not explicitly explore the role of instant messaging forensics in detecting corporate fraud [7-10]. One of the most promising areas in instant messaging forensics is conversation data analytics, which involves the algorithmic analysis of textual and non-textual elements within chat conversations. Kim and Lee (2016) were among the pioneers to integrate natural language processing (NLP) tools into fraud detection, highlighting the potential of keyword frequency as a predictor of fraudulent intent. Johnson and Gupta (2018) took this a step further by employing machine learning algorithms to categorize patterns of conversation that correlate with fraudulent activities. Their study, however, raised questions about the use of conversation data analytics in various sectors outside policing sector, a concern later echoed by Davis and Williams (2019).

But while these studies showed promising outcomes, they also revealed significant gaps in the field. For instance, Smith et al. (2017) pointed out the absence of standardized protocols for analyzing conversation data. They noted that the forensic community has yet to agree on the metrics and tools to be used, creating inconsistencies in the quality and reliability of the findings. Moreover, the issue of false positives and negatives was raised by Thompson and Smith (2020), who found that current algorithms could erroneously flag innocuous conversations as suspicious. Another critical aspect of instant messaging forensics is the analysis of unencrypted data. Because they are not protected by cryptographic algorithms, unencrypted messages and files are easier to intercept and scrutinize. Williams (2016) provided empirical evidence suggesting that unencrypted data often yield quicker results in fraud investigations due to the reduced need for decryption. Davis et al. (2017) supported this view by empirically showing that the absence of encryption not only facilitates faster analysis but also increases the accuracy of the results. However, the ethical implications of this approach have been a significant concern. Brown and George (2018) delved into the ethical dimensions of scrutinizing unencrypted data, especially where third parties are involved. They argued that the ease of access to such data raises questions about privacy and consent, issues that the forensic community has yet to fully resolve. Furthermore, Yang and Zhang (2019) noted that with the growing adoption of end-to-end encryption in corporate communications, the future relevance of unencrypted data analytics is becoming increasingly uncertain [11-16].

The final component under review is contact data analytics, which focuses on analyzing an individual’s network of contacts within the instant messaging environment. Zhang et al. (2015) were among the first to illustrate the effectiveness of this approach in identifying fraudulent networks within organizations. Their empirical study used basic statistical methods to map out contact frequencies and durations, thereby identifying potential key players in fraudulent activities. This methodology was later refined by Thompson and Smith (2020), who integrated machine learning algorithms to reduce false positives and negatives. However, despite these advancements, the field of contact data analytics still has significant gaps. For example, Yang et al. (2021) pointed out that existing methodologies are prone to generating false positives, which can have severe legal consequences. Additionally, the ethical aspects of contact data analytics remain underexplored. Questions about data ownership, consent, and the potential for misuse are yet to be adequately addressed, as noted by Wilson and Davis (2020). The empirical literature on the role of instant messaging forensic investigations in the detection of corporate fraud reveals several critical gaps that warrant further study, particularly within the context of commercial banks in Kenya. First, there is a pressing need for testing the applicability of instant messaging forensics in various contexts using the developed standardized protocols and methodologies. Existing research highlights the inconsistency in the tools and metrics employed, leading to variable quality and reliability in outcomes. Second, ethical concerns, especially concerning unencrypted and contact data analytics, remain largely unaddressed. These ethical dilemmas become more pressing in a banking environment where confidentiality and privacy are paramount. Third, the legal admissibility of evidence generated from instant messaging forensics is still a grey area, a critical concern in the prosecution of fraud cases. Fourth, the rapid adoption of encryption technologies raises questions about the future utility of certain types of data analytics, particularly unencrypted data analytics. Lastly, there is a notable lack of comprehensive methodologies capable of minimizing false positives and negatives, an issue that could result in wrongful accusations or overlooked fraudulent activities. Given that commercial banks are integral to Kenya’s economy and are susceptible to sophisticated fraudulent schemes, addressing these gaps becomes vital for enhancing the effectiveness and reliability of fraud detection mechanisms within this sector [17-25].

Materials and Methods

Study design

This research employed a descriptive design to investigate the role of instant messaging forensics in detecting corporate fraud within the Kenyan banking sector. The study encompassed 43 Kenyan banks and also included the Banking Fraud Investigation Department (BFID) at the Central Bank of Kenya (CBK). The target population consisted of 390 individuals, specifically digital forensics managers and officers working within these banks and the BFID, all of whom are directly involved in handling cases of corporate fraud requiring digital forensic investigation.

Sampling methodology

A total sample size of 114 digital forensic officers, representing both the banks and the Central Bank of Kenya, was selected for this study. Stratified proportionate sampling techniques were used to divide respondents into two categories: officers and managers from both the banks and BFID. In addition, purposive sampling was used to select participants with specific expertise in digital forensics within these institutions. To address the study’s sensitive nature and encourage participation, a snowballing technique was employed, leveraging existing relationships and referrals to gain the trust and cooperation of prospective respondents [26-34].

Data collection instruments and procedure

Data collection relied exclusively on a Likert-type questionnaire, composed of 5-point scale questions, aimed at gathering insights on various facets of instant messaging forensics, including conversation data analytics, contact data analytics, unencrypted analytics, as well as fraud detection in banks. Questionnaires were distributed and administered through a combination of drop-and-pick methods and face-to-face interviews. The latter were also employed for conducting semistructured interviews. To ensure the instrument’s reliability and validity, a pilot study was conducted involving 11 respondents from the Criminal Investigation Department’s fraud investigation unit. Content validity was ascertained by incorporating questions directly related to the constructs being measured, while face validity was enhanced through consultations with subject matter experts and academic supervisors. The internal consistency of the questionnaire was evaluated using Cronbach’s alpha test.

Data analysis

Completed questionnaires were coded and entered into SPSS software (version 24) for analysis. Given the use of close-ended questions, data entry was streamlined and efficient. Data was first cleaned and coded, followed by descriptive statistical analysis using frequencies and percentages to summarize respondent profiles. Multiple regression techniques were employed to assess the relationship between digital forensics methods and fraud detection, thereby testing the study’s objectives [35-40].

Results

Respondent profiles in terms of work experience

Table 1 results shows that about half of the respondents (50.5%) have between 9 to 12 years forensic investigation experience followed by those who had more than 12 years of experience (29.7%). 13.2% of the respondents had between 5- 8 years of experience while 6.6% had less than 5 experience. These results imply that significant portion of the respondents had experience on forensic investigation.

Regression results

The results in table 2 shows the relationship between digital forensics technologies and fraud detection in banks. The dependent variable is fraud detection in banks, while the independent variables are conversation data analytics, contact data analytics and unencrypted data analytics. The results indicate that conversation data analytics (p =0.001) and unencrypted data analytics (p =0.003) have a significant positive impact on fraud detection in banks. On the same note, conversation data analytics has the highest contribution (β= 0.308) to fraud detection followed by unencrypted data analytics (β= 0.226) and contact data analytics (β= 0.016) [41-45].

Discussion of Findings

The study found that conversation data analytics has a significantly positive impact on fraud detection in banks, as indicated by a p-value of 0.001 and a beta coefficient of 0.308. This result aligns with previous scholarly work, such as the study by Johnson and Gupta (2018), which found that machine learning algorithms could effectively categorize patterns of fraudulent conversations. The strong beta coefficient of 0.308 suggests that among the variables studied, conversation data analytics is the most potent predictor of successful fraud detection. The study also revealed that unencrypted data analytics has a significant positive impact on fraud detection, with a p-value of 0.003 and β=0.226. This supports Davis et al. (2017), who noted that unencrypted data often yield quicker and more accurate results in fraud investigations. The result also underscores the importance of unencrypted data analytics in the banking sector, suggesting that it is a valuable but slightly less influential tool compared to conversation data analytics for combating fraud. Contrary to expectations, contact data analytics showed a very minimal impact on fraud detection in banks, with a β value of 0.016. This is surprising given prior research, such as the study by Zhang et al. (2015), which found contact data analytics useful in identifying fraudulent networks within organizations. The unexpected result in our study raises the question of whether the role of contact data analytics in fraud detection is context-dependent or influenced by other variables not considered in this study.

Conclusion

The current study provides an understanding of the role of instant messaging forensics investigation on fraud detection within commercial banks, particularly focusing on the Kenyan context. Our empirical findings indicate a significant positive relationship between conversation data analytics and fraud detection. Similarly, unencrypted data analytics also emerged as a significant predictor of successful fraud detection, albeit to a lesser extent. Surprisingly, contact data analytics demonstrated a minimal impact. These findings offer both academic and practical implications. From an academic standpoint, the study validates the significance of conversation and unencrypted data analytics in fraud detection, while raising questions about the role of contact data analytics that warrant further investigation. Practically, the results suggest that commercial banks in Kenya would benefit from investing more heavily in conversation and unencrypted data analytics technologies for more effective fraud detection. Given the increasing sophistication of fraud schemes, adopting such advanced forensic methods appears to be not just beneficial but essential for ensuring the financial integrity of banks.


To Know more about Journal of Forensic Sciences & Criminal Investigation
Click here: https://juniperpublishers.com/jfsci/index.php

To Know more about our Juniper Publishers

Understanding The Acute Interventions for Complicated Pleural Effusions - Juniper Publishers

  Pulmonary & Respiratory Sciences - Juniper Publishers Abstract Pleural effusion affects approximately 1.5 million individuals in the U...