Tuesday, October 17, 2023

Three Pharmacological Models: Inducing Inflammatory Bowel Disease and Colitis-Associated Cancer - Juniper Publishers

 Gastroenterology & Hepatology - Juniper Publishers


Abstract

Colorectal cancer (CRC) is a kind of incurable cancer with high morbidity and mortality. In recent years, mounting evidence has revealed that inflammatory bowel disease (IBD) was correlated with colitis-associated cancer (CAC). Signal transduction is an effective way for cells to respond to external stimuli and eventually trigger specific biological effects. The occurrence, growth and metastasis of cancer are usually associated with disorders of signaling pathways. Although modern research can elucidate the pathogenesis of CAC and provide enhanced screening strategies, the prevalence of CAC is still rising. Studies have shown that several cells signaling pathways in CAC are dysfunctional, leading to the occurrence of malignant phenotypes. Therefore, analyzing the signaling pathways involved in CAC metastasis is necessary to elucidate the potential mechanisms of CAC progression and drug treatment. Our understanding of CAC-related signaling pathways is largely due to a mouse model that faithfully reproduces human CAC. In particular, chemical models can quickly and effectively analyze the molecular mechanism of CAC without increasing time-intensive genetic hybridization. Therefore, this article summarizes the following three chemical-induced CAC animal models, azoxymethane/dextran sodium sulfate (AOM/DSS), 1, 2-dimethylhydrazine (DMH)/DSS and 2, 4, 6-trinitrobenzene sulfonic acid (TNBS)/AOM. Among them, DSS and TNBS were used as inflammatory agents to simulate the pathogenesis of IBD inflammatory models, while AOM and DMH were used to producing carcinogenic methylated DNA, combined with inflammatory agents, could better induce IBD to CAC in animals.

Keywords: Colitis-associated cancer; Inflammatory bowel disease; AOM/DSS; DMH/DSS; TNBS/AOM

Abbreviations: CRC: Colorectal Cancer; IBD: Inflammatory Bowel Disease; CAC: Colitis-Associated Cancer; AOM: Azoxymethane; DSS: Dextran Sodium Sulfate; DMH: 1, 2-Dimethylhydrazine; TNBS: 2, 4, 6-Trinitrobenzene Sulfonic Acid; ACF: Abnormal Crypt Foci; UC: Ulcerative Enteritis; CD: Crohn’s Disease; MAM: Methylazomethanol; ROS: Reactive Oxygen Species; MDSC: Myeloid-Derived Suppressor Cells; DC: Dendritic Cells; Th: T Lymphocytes; MyD88: Myeloid Differentiation Factor 88; CPB: CREB Binding Protein; GR: Glutathione Reductase; HO-1: Heme Oxygenase-1; TR: Thioredoxin Reductase; PEITC: Phenethyl Isothiocyanate; GSK3β: Glycogen Synthase Kinase 3β; CK1α: Casein Kinase 1α; DVL: Disheveled; TCF: T Cell-Specific Factor; LEF: Lymphoid Enhancer Binding Factor; MDF: Mucin-Depleted Foci; JAK2: Janus Kinase 2; STAT3: Signal Transducer and Activator of Transcription 3

Introduction

Colorectal cancer (CRC), as one of the common malignancies with high morbidity and mortality [1,2], usually occurs at the junction of the rectum and sigmoid colon. It is the result of healthy colonic epithelial cells transforming into cancer [3]. This process is called ‘adenoma-carcinoma sequence’, which is developed through a series of orderly events. The initial step is the transformation of normal colonic epithelium to abnormal crypt foci (ACF). ACF progresses to CRC within 10-15 years [4,5]. Accumulating evidence has shown that its occurrence and development were related to many factors, such as environment, eating habits, congenital heredity, personal physique and so on [6]. Over the past few decades, CRC, including colitis-associated cancer (CAC) has posed a serious threat to people’s health and life, which develops from long-term colitis in inflammatory bowel disease (IBD) patients [7] .

IBD, one of the key influential factors resulting in CAC, is a chronic and recurrent gastrointestinal inflammatory disease that can affect the body’s immune mechanism [8]. Generally speaking, the occurrence of IBD in humans may be related to environmental factors [9]. but in the current research hotspots, diet is also considered to be the cause of IBD to a certain extent [10]. especially the intake of allergenic substances in food [11]. Clinically, IBD is usually divided into two kinds of disease, ulcerative enteritis (UC) and Crohn’s disease (CD) [12,13]. Studies have found that long-term IBD may not only lead to the occurrence and development of CRC, but also increase the risk of prostate cancer [14]. gastric cancer and other cancers [15]. Morever, the risk of colorectal cancer is increased twofold in CD and in UC [16] while about 8% of UC patients develop CAC within 20 years and 18% within 30 years [17].

The rodent carcinogen-induced model recalls a long tradition but still retains its usefulness for some applications. They provide a platform for dietary research and insight into the pathways of food-borne carcinogens and colitis-related carcinogenic effects. Since the development of carcinogen-induced rodent models for CAC more than 80 years ago, these animal models have played a huge role in chemoprevention research and assessment of colitisrelated carcinogenic mechanisms [18]. In 1915, scientists proved the carcinogenic properties of coal tar by repeatedly applying coal tar to rabbit ears [19].

At about the same time, the first researchers studied the occurrence of colon cancer by applying chemical or radioactive substances [20]. In the 1960s, heme and its metabolite methylazooxymethanol have been shown to induce rodent cancer [21,22]. In the following years, the chemically more stable substance AOM and its precursor DMH were widely used to induce colon cancer in mice and rats. Both of the two compounds are metabolized to methylazoformaldehyde, which can alkylate DNA bases guanine and thymine [23]. After two-phase reaction treatment, it is secreted into the bile, and its carcinogenic effect on intestinal mucosa exceeds its carcinogenic effect [24].

The most typical AOM/DSS model needs to be combined with a single injection of AOM, a carcinogen that is metabolized in the liver to the active agent methylazomethanol (MAM), and then use inflammatory damage agent DSS [25]. The pathological manifestations of the AOM/DSS model were severe colitis, accompanied by weight loss and bloody diarrhea, and followed by multiple colon tumors. Another carcinogen DMH undergoes a series of metabolic reactions and eventually reaches the colon, producing the ultimate carcinogen and reactive oxygen species (ROS), which further alkylate DNA and cause colon cancer [26]. TNBS, a classical skin contact ant serves as a happen, which could induce a specifically inflammation model in the gastro-intestinal tract [27].

It was reported that the exact location of tumor in colon length depends on the mouse strain and background [28]. The carcinogenic process of the system has a pathological progression from normal intestinal crypts to crypt fission to lesions with abnormal crypts and eventually to microadenomas [29,30]. These steps outline the sequence of CAC formation in humans from inflammation to developmental abnormalities and to cancer.

In recent years, AOM/DSS [31-33] DMH/DSS [34,35] and TNBS/AOM [36,37] are three main methods to establish CAC animal models, as these three chemical pathways could better simulate the process of IBD to CAC in vivo. Therefore, this paper summarized the mechanism of these three modeling methods which can reflect IBD and CAC as follows.

AOM/DSS

Chemical properties

AOM is a class of chemical compound with the molecular formula of C2H6N2O (molecular weight: 74.08g/mol) and strong oxidative activity. DSS is a kind of polyanion derivative of dextran with the chemical formula of (C6H7Na3O14S3) n), which could be used for modeling CAC, separating lipoproteins and improving nucleic acid hybridization rate.

Modeling method

AOM/DSS model is the most widely used and reproducible method to induce CAC. Mice were intraperitoneally injected with AOM (7mg/kg or 12.5mg/kg) [38]. After 5 days, mice received 3 cycles of drinking 1%-3% DSS solution for 5 days and water for 14 days [39]. At the end of the experiment, the mice showed obvious intestinal polyps with intestinal mucosal injury.

Mechanism

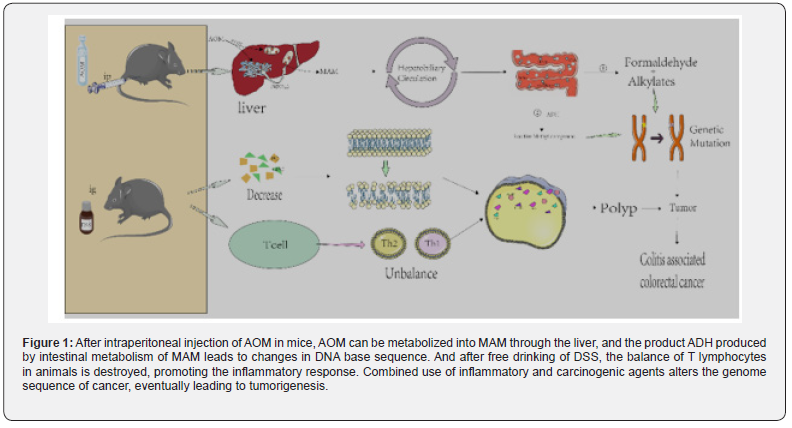
As shown in figure 1, AOM reaches the liver through blood circulation. Under the action of cytochrome P4502E1 [40,41]. it is hydroxylated to form MAM [42]. which can spontaneously decompose into formaldehyde and highly active alkylate after entering the intestine [43]. In addition, some scholars have proposed that MAM may be metabolized through another pathway, that is, the metabolic reaction involving tissue-specific cytoplasmic enzyme ADH in the intestine.

ADH generates reactive methylases, alkylases, or such reactive methylases, which can promote DNA alkylation [44,45], and subsequently induce DNA to produce O6-methylguanine adduct [46], resulting in the conversion of G to A in the DNA base sequence. MAM through the liver, and the product ADH produced by intestinal metabolism of MAM leads to changes in DNA base sequence. And after free drinking of DSS, the balance of T lymphocytes in animals is destroyed, promoting the inflammatory response. Combined use of inflammatory and carcinogenic agents alters the genome sequence of cancer, eventually leading to tumorigenesis. AOM/ DSS is one of the most commonly used chemical reagents to induce CAC in rodents [47] which can better simulate the pathological process of the body from normal intestinal epithelial mucosa to abnormal crypt lesions [48] adenoma and colorectal cancer [49].

Among them, DSS reagent has the characteristics of convenient use and high efficiency [50], as a chemical reagent for inflammatory stimulation, it continuously stimulates the mucosa of intestinal epithelial cells during free drinking, causing repeated inflammation in model animals. In the DSS model, sulfated polysaccharides do not directly induce intestinal inflammation, but act as a direct chemical toxin of colonic epithelium, leading to epithelial cell damage. The mechanism is that oral administration of DSS leads to the destruction of the intestinal epithelial monolayer lining, the entry of intraluminal bacteria and associated antigens into the mucosa, and the transmission of pro-inflammatory intestinal contents to the lower tissues [51-53].
It is generally believed that in chronic inflammation, the immune system is characterized by intensive infiltration of innate immune cells (such as macrophages, neutrophils, myeloidderived suppressor cells (MDSC), dendritic cells (DC) and NK cells and adaptive immune cells (such as T and B lymphocytes), further suggesting that the changes in the intestinal inflammatory microenvironment promote tumor formation [29] In the internal environment of the body, helper T lymphocytes (Th) play an important role in the immune response. The dynamic balance of Th1 and Th2 is one of the necessary conditions to maintain the normal physiological function of the body [54]. Therefore, the increase or decrease of Th1 or Th2 could cause immune response [55] eventually resulting in the occurrence of inflammation [56,57].

After oral administration of DSS in mice, the dynamic balance between Th1 and Th2 was broken, which promoted the expression of inflammatory factors such as TNF-α, IL-1β, IL-10 and IFN-γ, and so on [58,59]. In AOM/DSS model animals, the continuous production of pro-inflammatory cytokines leads to mutations in proto-oncogenes and tumor suppressor genes APC, K-RAS and p53, as well as genomic sequence variations, generating tumorigenesis, progression and metastasis [60]. Myeloid differentiation factor 88 (MyD88), a molecule essential for TLR intracellular signaling, appears to have a protective effect against AOM/DSS-induced inflammation-associated CRC in mice [61]. Yassin M proposed that AOM/DSS-induced inflammation led to an increase in the total number of CD3+, TCRγδ and TCRαβ cells, including a significant increase in CD4+TCRαβ cells, but only moderate changes in CD8αβ TCRαβ and CD8αβ TCRαβ/TCRγδ cells. This suggests that CD4+T cell recruitment plays a key role in regulating various parts of the mucosal immune response during acute and chronic DSS-induced colitis [62].

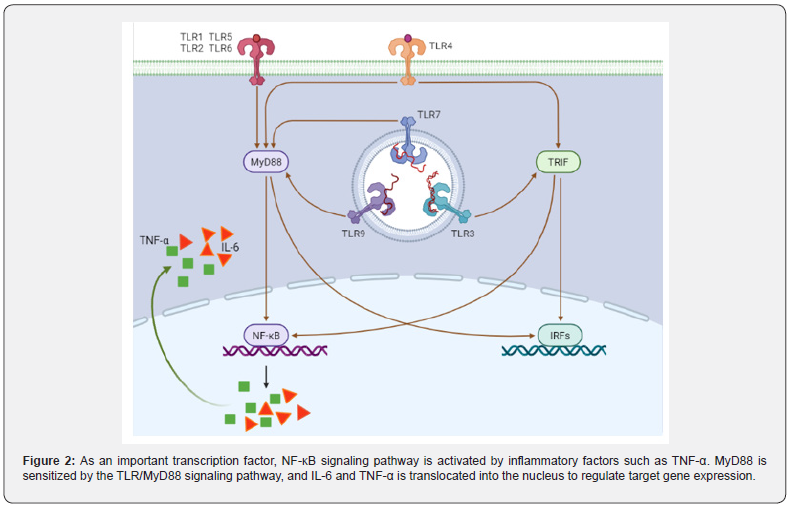
The NF-Κb signaling pathway, a central mediator between inflammation and cancer, promoting CAC development: It is well known that TNF-α can directly activate NF-κB signaling pathway and induce inflammatory response. Furthermore, MyD88 signaling molecules can also activate NF-κB-induced kinase and indirectly activate NF-κB signaling pathway through TLR/MyD88 signaling pathway [63,64] (Figure 2). Xie et al. [65] synthesized a MyD88 inhibitor TJ-M2010-5, which can bind to the TLR domain of MyD88, inhibit the production of its homodimer, and ultimately inhibit the TLR/MyD88 signaling pathway. TJM2010- 5 can significantly reduce the incidence of AOM/DSSinduced colitis, shorten colon length, reduce tumorigenesis, and inhibit the production of inflammatory factors. Moreover, when the TLR4-deficient mice and the wild-type mice were treated with AOM/DSS at the same time, it was observed that the TLR4- deficient mice had a lighter degree of colon cancer than the wild type mice [66]. After the MyD88-/- mice were injected with AOM, colonoscopy showed no tumor formation in the intestine, and the mRNA expression of pro-inflammatory cytokines TNF-α and IL12P40 was lower than that of the model group [67]. On the one hand, the production of TNF-α can activate the NF-κB signaling pathway, on the other hand, when the NF-κB signaling pathway is activated, it can also promote the transcription and translation of TNF-α. El-Daly et al. [68]. showed that in AOM/DSS-treated mice, the positive staining of p65 in the nucleus of the vagus nerve crypt of colorectal epithelial cells gradually increased with the increase of DSS administration cycle. In addition, AOM/DSS also induced the high expression of TLR4 and p65 proteins upstream of NF-κB signaling pathway. Furthermore, Song et al. [69]. found that the expression level of pro-inflammatory enzyme COX-2, which is mainly regulated by NF-κB signaling pathway, was significantly higher than that of the control, and the expression levels of the other two target genes TNF-α and IL-6 also tended to increase [70].
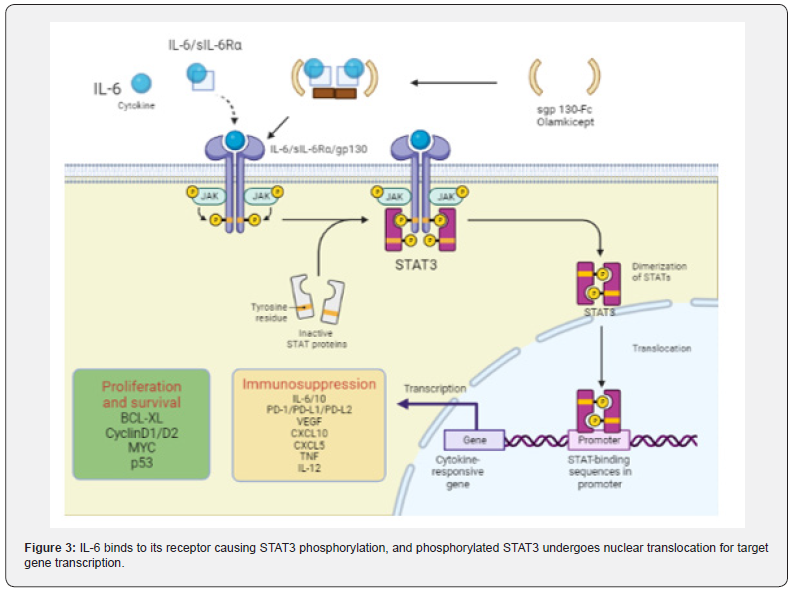
The IL-6/STAT3 signaling pathway is enhanced and accelerates carcinogenesis in CAC: As an inflammatory cytokine, IL-6 binds to soluble IL-6 receptors to form an IL-6/ sIL-6R complex [71,72]. which activates gp130 expression on the cell membrane, leading to signal transducer and activator of transcription 3 (STAT3) phosphorylation. STAT3 enters the nucleus in the form of dimers and activates the STAT3 signaling pathway (Figure 3) [73]. Studies have shown that p-STAT3 staining in the colorectal region of AOM/DSS-treated mice was deepened, and the deposition of brown granules in cytoplasm and nucleus was enhanced with the increase of the administration cycle [74]. MiR-18a is a transcription product in the STAT3 signaling pathway, in AOM/DSS-treated mice, it was found that the expression of MiR- 18a increased significantly with the extension of DSS treatment cycle [75]. but the expression of PIAS3 (an inhibitor of STAT family activation) decreased. In vitro studies have shown that the expression level of MiR-18a is negatively correlated with PIAS3. MiR-18a can negatively regulate PIAS3 [76]. while overexpression of PIAS3 leads to a decrease in IL6-activated STAT3 activity. Ma et al. reported that the proliferation and survival of precancerous intestinal epithelial cells (IECs) were regulated by IL-6/STAT3 signaling pathway, and CAC may be related to this signaling pathway [77].

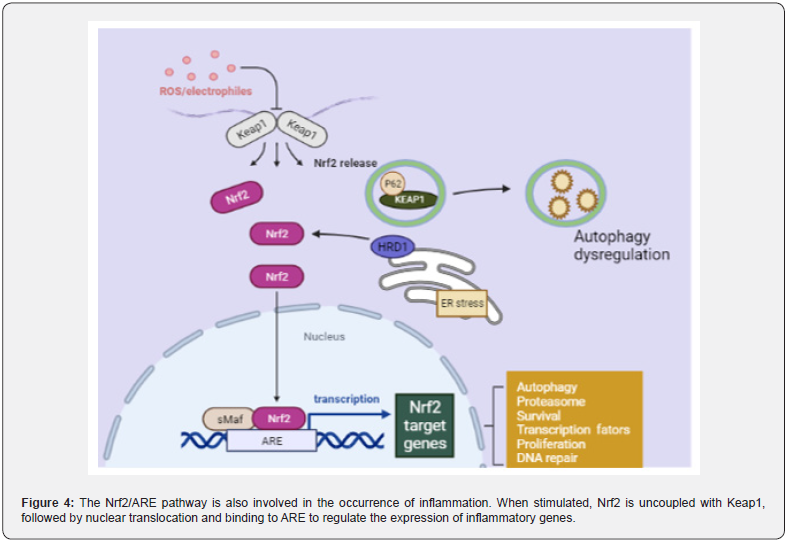
Nrf2/ARE signaling pathway plays an inflammatory role in CAC: In addition, the occurrence of inflammation is also related to the activation of the antioxidant Nrf2/ARE signaling pathway. When the Nrf2/ARE signaling pathway is closed, Keap1 in the cytoplasm specifically binds to the N-terminus of Nrf2, thereby maintaining the normal physiological function of the body. However, when cells receive external stimuli, the Nrf2/ARE signaling pathway is immediately activated, Nrf2 is uncoupled with Keap1, and then enters to the nucleus and binds to the small may protein to form a heterodimer. This process requires the participation of transcription cofactor CREB binding protein (CPB).

Heterodimers specifically recognize ARE and initiate transcription and translation of target genes, resulting in inhibition of the Nrf2/ARE signaling pathway (Figure 4). When the antioxidant process in the body is initiated, the expression of antioxidant proteins is significantly increased to protect cells from damage [78,79]. Wang et al. [80]. found that the positive expression of Nrf2 and the expression of glutathione reductase (GR), heme oxygenase-1 (HO-1) and thioredoxin reductase (TR) were significantly degraded in AOM/DSS treated mice. The researchers [81]. fed mice with 0.05% phenethyl isothiocyanate (PEITC) before and after AOM/DSS administration, found that the incidence of intestinal adenomas in mice decreased by 37.5% and 40%, the number of polyps reduced to 0.375 and 0.6, and the average size decreased to 1.5 and 2.6 mm, respectively. It can be inferred that PEITC can improve the development of intestinal tumors, as an activator of Nrf2, PEITC can activate Nrf2/ARE signaling pathway. In addition, some scholars performed Nrf2 gene knockout in wild AOM/DSS model mice, early model mice and 9-week model mice [82]. It was proved that Nrf2-/- mice showed the same phenotype as wild-type mice, but the incidence of tumors and the proportion of adenocarcinoma were higher.
DMH/DSS

Chemical properties

DMH is a class of compound whose molecular formula is C5H8N2O2 (molecular weight: 128.13g/mol) and provides raw materials for the synthesis of proteins in vivo.

Modeling method

Scientists [83] injected DMH (40mg/kg) into FMH rats three times in the first week, and then gave 1% DSS solution to drink freely for one week, repeating three cycles. DMH is a precursor of the carcinogen AOM, which is not carcinogenic in itself, but can be carcinogenic by oxidative dealkylation to form AOM [84]. The study confirmed that DMH-treated rats had traditional tubular or villous adenomas and serrated adenomas [85] in their colorectal regions, and it is generally believed that most colorectal cancers progress from adenomas.
Mechanism

As a proto-oncogene, DMH can be decomposed into azomethane and methylazomethanol under the catalysis of liver enzyme system. The latter substance flows to the colon tissue through the hepatobiliary circulation and is easily decomposed into a carcinogen methyl diazo ion [86] in the circulation. Methyl diazo ions can methylate DNA, RNA and proteins in normal intestinal epithelial cells. When they reach the colorectal site, they can produce activated carbon ions, leading to oxidative stress, over-expression of inducible nitric oxide synthase (i-NOS) and COX-2 [87], which in turn causes colorectal cancer.

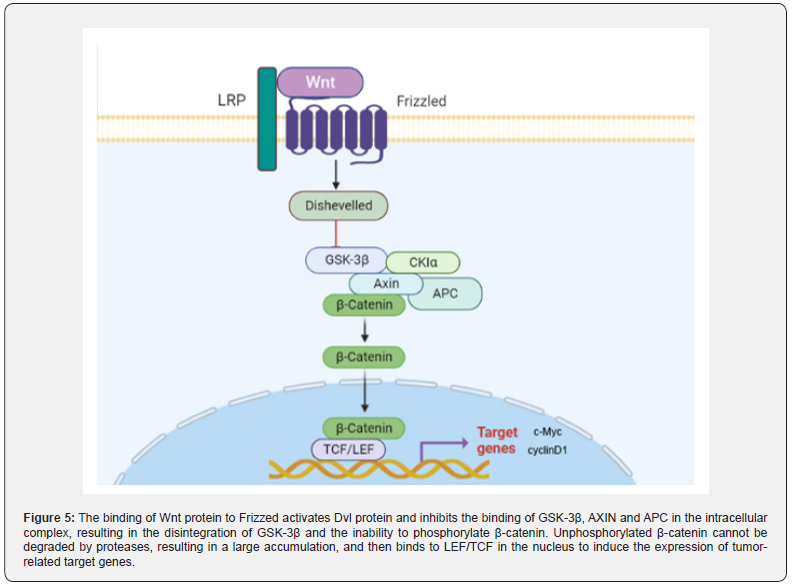
Up-regulated Wnt/ β -catenin signaling pathway promotes CAC progression: Wnt/β-catenin signaling pathway is a conserved signaling axis involved in a variety of physiological processes, such as proliferation, differentiation, apoptosis, migration, invasion and tissue homeostasis [88,89]. In the Wnt/β-catenin pathway, the abnormal regulation of the transcription factor β-catenin can lead to the occurrence of early cancer events [90,91]. In the degradation complex of this pathway, glycogen synthase kinase 3β (GSK3β) and casein kinase 1α (CK1α) mediate phosphorylation of β-catenin, promoting its ubiquitination and subsequent proteasome degradation [92]. The β-catenin dependent signaling pathway is triggered by the binding of secreted cysteine-rich glycoprotein ligands Wnts to LRP-5/6 receptors and FZD receptors. In the presence of Wnt ligands, the binding of Wnt ligands on the cell surface to the receptor induces disheveled (DVL), leading to the aggregation of complexes (AXIN, GSK3β, CK1, APC) to the receptor [93]. Subsequently, phosphorylation and inhibition of GSK3β ensured an increase in cytosolic β-catenin concentration. Unphosphorylated β-catenin in the cytosol migrates to the nucleus and accumulates, interacting with T cell-specific factor (TCF)/lymphoid enhancer binding factor (LEF) to trigger Wnt target genes such as c-Myc [94]. and cyclin D1 (95), resulting in up-regulation of TCF/LEF target genes [95].

In the analysis of 11 DMH/DSS-induced adenocarcinoma mice, Tanaka observed markedly enhanced expression of the β-catenin gene in 10 of 11 mice [96]. Furthermore, mutations of β-catenin, Apc and K-ras genes and cytoplasmic β-catenin expression were found in DMH-induced mucin-depleted foci (MDF) [97,98]. MDF is a microscopic dysplasia induced by specific colon carcinogens in the colon of rodents. Most MDF show Wnt pathway activation, while only one subset shows Ctnnb1 gene mutation, encoding β-catenin [99]. It is well known that β-catenin is a key upstream regulator of the Wnt signaling pathway. The activation of Wnt signaling pathway can lead to the increase of β-catenin into the nucleus (Figure 5), which leads to the increase of transcription of tumor-related factors and induces the occurrence of tumors in vivo.
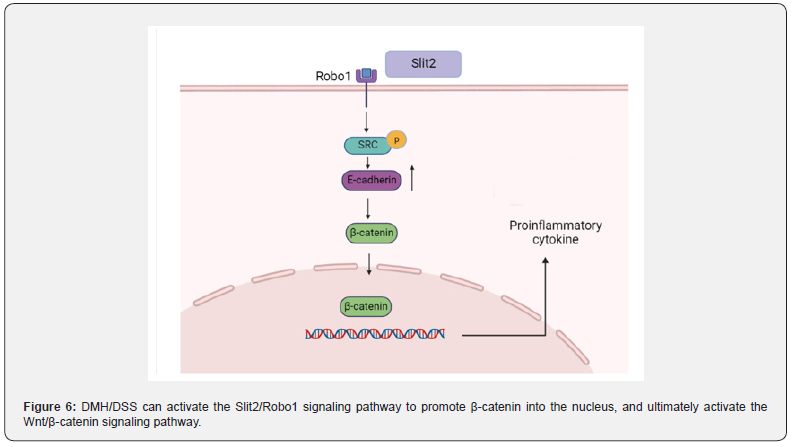
The Slit2/Robo1 signaling pathway induces the Wnt/β -catenin signaling pathway dysregulation to promote CAC progression: Slit/Robo signaling pathway includes Slit secreted protein family (Slit1, Slit2, Slit3) and specific receptors (Robo1, Robo2, Robo3, Robo4). The Slit2/Robo1 signaling pathway was initially found to be involved in the development of the central nervous system. In recent years, more and more studies have reported that it can induce tumorigenesis and participate in the proliferation and migration of tumor cells [100]. The activation of Slit2/Robo1 signaling pathway can be caused by ectopic expression of Slit2 protein (Figure 6). The Slit2 and Robo1 genes on chromosomes are located respectively at 4P15.2 and 3P12.3, Robo1 is a specific receptor of Slit2 [101]. The extracellular IgG region of Robo1 is an important position for binding to Slit2, and the intracellular region is a site for interaction with related signal molecules, which is involved in activating the downstream of Slit2/Robo1 signaling pathway and promoting the occurrence and development of tumors [102].

DMH/DSS can not only directly activate the Wnt signaling pathway, but also indirectly activate the Wnt signaling pathway by activating the Slit2/Robo1 signaling pathway Qian et al. [103]. found that the expression of Slit2 and Robo1 in DMH/DSS mice gradually increased with time. Morever, seven pairs of CRC tissues and non-cancerous colon tissues were randomly selected from patients with N0 CRC (no metastasis). The expression profiles of Slit2 and Robo1 were evaluated by immunohistochemical staining. It can be seen that the expression of Slit2 and Robo1 in CRC tissues is significantly higher than that in non-cancerous colon tissues. As long as the Slit2/Robo1 signaling pathway is activated, it can promote the activation of Src phosphorylation, resulting in increased expression of E-cadherin, thereby activating the Wnt/β-catenin signaling pathway, promoting β-catenin into the nucleus, leading to an increased expression of tumor-associated proteins.

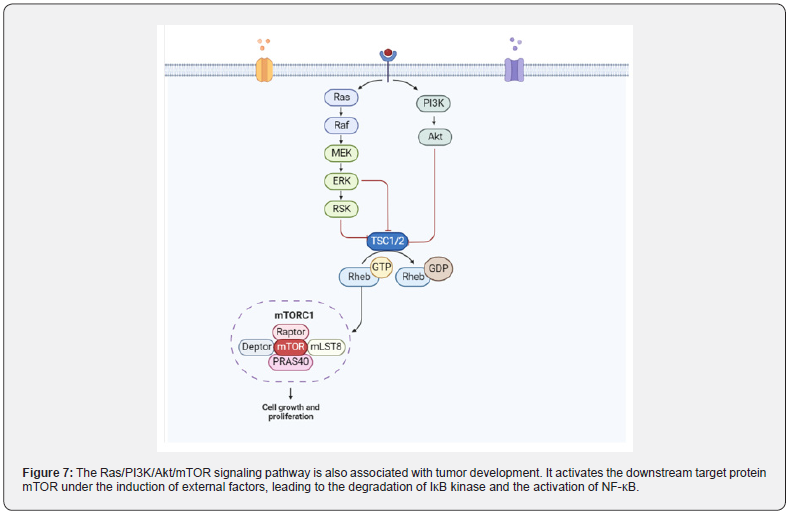
The Ras/PI3K/Akt/M TOR signaling pathway promotes the development of CAC by activating NF-κB protein: The carcinogenic activation of Ras protein caused by missense mutations is a well-known marker of tumor cell proliferation. Balb/c mice treated with DMH/DSS resulted in a significant increase in Ras protein levels. Activated Ras protein targets MEK to trigger ERK phosphorylation and nuclear translocation to express genes involved in cell proliferation. The levels of activated MEK1/2 and phosphorylated-ERK1/2 was significantly increased in DMH/ DSS-treated animals. In addition, Ras oncoprotein also interacts with PI3K and triggers Akt phosphorylation and subsequent activation. DMH/DSS-treated animals showed significantly increased levels of PI3K and phosphorylated Akt. The expression of NF-κB, a downstream effector of Akt, was also significantly increased. The authors believe that the increased expression of NF-κB can be attributed to chronic inflammation followed by circulatory treatment with the inflammatory agent DSS [104]. The mutation of RAS protein is induced by some external factors [105], and mutant RAS protein interacts with PI3K and causes autophosphorylation of PI3K. Type I PI3K is a heterodimer, the corresponding domain of the P85 subunit on the dimer can interact with the linker protein to recruit the corresponding activation receptor for PI3K, thereby converting PI3K into PIP2 and then into PIP3. PIP3 binds to Akt and PDK1 containing the PH domain, leading to the activation of Akt, which in turn regulates the expression of its downstream target protein mTOR. On the other hand, this binding can also activate IK-B, thereby relieving the inhibition of NF-κB, transferring NF-κB from the cytoplasm to the nucleus, and finally regulating the expression of inflammatory factors in the epidermis (Figure 7).
TNBS/AOM

Chemical properties

TNBS is a kind of dangerous chemical compound with a molecular formula of C6H3N3O9S (molecular weight: 293.17). In bioengineering, TNBS can be carried out determining aminoterminal groups, hydrophilic modification reagents, etc.

Modeling method

Xiao et al. [37] injected AOM (10mg/kg) intraperitoneally into C57BL/6 mice, and then 2.5mg TNBS was dissolved in 150μl 50% ethanol and injected into the mice through the rectum. The changes of intestinal tumors in mice were observed under rectal endoscopy. TNBS-induced colitis is very similar to CD, which can induce transmural colitis (Th1-mediated immune response) with severe diarrhea, weight loss, rectal prolapse [106,107], tissue destructive and recurrent [108].

Mechanism

Normally, TNBS was used in combination with anhydrous ethanol. By enema administration, the intestinal mucosa of the model animals was damaged, so that TNBS penetrated the intestinal wall, combined with the related proteins in the intestine, and caused the intestinal epithelial mucosaltenization. Therefore, intestinal cells are more likely to expose target proteins, stimulate immune cells above the intestinal lamina propria [109], and make target proteins more easily recognized by immune cells [110]. resulting in acute necrosis.
TNBS promotes the expression of the same T cytokines as CD [111]. which is an immune inflammatory disease mediated by Th1 [112]. However, the Th1-mediated cycle is short and mainly mediated by Th17, which is characterized by infiltration of CD4+T cells in the intestine [113]. and severe fibrosis of intestinal wall cells in advanced patients [114]. Alrafas Haider [115] treated TNBS-induced colitis with resveratrol and found that the induced inflammatory T cells (Th17 and Th1), cytokines and transcription factors (Foxp3 and TGF-β) were significantly decreased, and the severity of colitis in mice was significantly increased. In general, TNBS-induced colitis also involves Th17-related cytokines [116].

More and more evidence suggests that the growth and proliferation of Th17 cells depend on IL-23. Therefore, some scholars have proposed that the IL-17/IL-23 axis may also be one of the causes of IBD [117,118]. Cubes [119]. found that I-NOS is associated with TNBS-induced colitis and can cause intestinal mucosal damage in model animals, which is similar to some features of DSS-induced colitis. The pathogenesis of CD induced by TNBS is not clear, but the mutation of NOD2 gene was found in C57 mice treated with TNBS, and the mutation of NOD2 gene is related to the pathogenesis of CD. Hence, it is concluded that TNBS can induce CD-related enteritis in model animals [120].

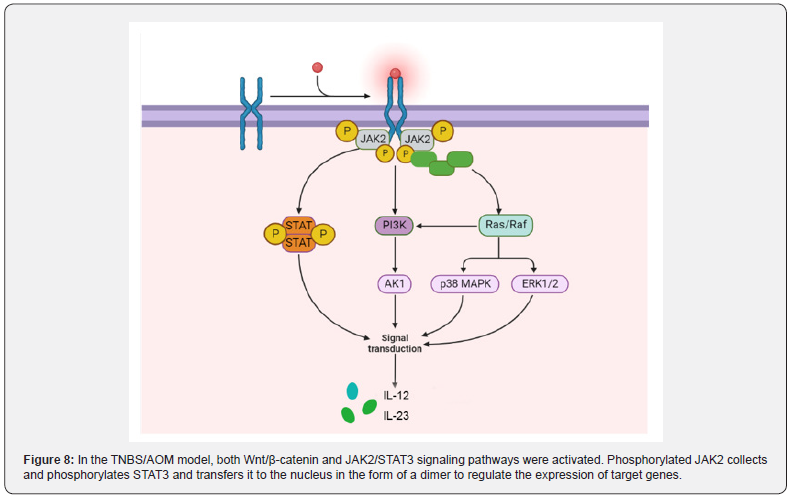
The JAK2/STAT3 signaling pathway plays an oncogenous role in the development and progression of CAC: JAK contains four tyrosine kinases (JAK1, JAK2, JAK3 and TYK2), while STAT contains seven transcription factors (STAT1, STAT2, STAT3, STAT4, STAT5A, STAT5B and STAT6). JAK2(Janus kinase 2)/STAT3 pathway is an important signal transduction pathway in the body, which plays a role in many physiological and pathological processes such as immunity, cell proliferation, differentiation, apoptosis and inflammatory response [121]. Under the stimulation of certain cytokines, JAK2 is activated, and then STAT3 is activated, which can transmit extracellular signal into the nucleus and regulate the expression of related inflammatory factors [122]. In the TNBS/ AOM animal model, the activation of Wnt/β-catenin and JAK2/ STAT3 pathways occurred with the development of colitis to adenoma.

He et al. [123]. confirmed that in TNBS-treated mice, Ang II was significantly elevated and the JAK2/STAT3 signaling pathway was activated to induce colitis by stimulating phosphorylation of JAK2 and STAT3. The colitis of TNBS mice treated with JAK2/ STAT3 pathway inhibitor tofacitinib was significantly improved. Lu et al. [124] found that TNBS can not only induce colitis, but also accompanied by visceral allergies. Subsequently, Wan [125] found that the expressions of JAK2, STAT3, p-JAK2 and p-STAT3 was upregulated in TNBS-treated goats. JAK2 is one of the four members of the JAK family located on the cell membrane, specifically binds to some transmembrane receptors and is phosphorylated by internal conformational changes. Phosphorylated JAK2 recruits a large number of STAT3, leading to STAT3 phosphorylation and nuclear translocation in the form of dimers, ultimately mediating the expression of downstream target genes (Figure 8).
The Wnt/β-catenin signaling pathway plays a tumorigenic role in CAC: Zhao et al. [126]. showed that the expression of TCF, β-catenin and Wnt upstream proteins in the TNBS group was significantly higher than that in the blank group, and the expression of tumor-associated proteins c-Myc and cyclinD1 was also significantly enhanced. In the Wnt/β-catenin signaling pathway, Wnt protein binds to the coiled protein (coiled gene) on the cell membrane. After seven trans membranes [127]. the signal is transmitted to the Dvl protein. Subsequently, the activation of Dvl protein inhibited the binding of intracellular complexes GSK-3β, AXIN and APC, resulting in the dissociation of GSK-3β, and then GSK-3β could not phosphorylate β-catenin [128,129]. Unphosphorylated β-catenin cannot be degraded by proteases, resulting in a large accumulation of β-catenin. This process promotes the entry of β-catenin into the nucleus, where it binds to nuclear LEF/TCF and induces the expression of tumor-associated target genes. Therefore, TNBS-induced colitis can complete the process from CD to CAC under the combined action of AOM.

The Other Mechanism of Three Pharmacological Models

Inflammation, endoplasmic reticulum stress and autophagy

It is confirmed that infection and a large number of inflammatory stimuli could cause endoplasmic reticulum stress and activate the UPR signaling pathway, mainly by promoting Ca2+ release from the endoplasmic reticulum and ROS accumulation. For example, pro-inflammatory cytokines IL-1β and IFN-γ can directly down-regulate the expression of Ca2+-ATPase (SERCA2) on the endoplasmic reticulum to depleted ER Ca2+ stores, thereby causing ERS [130].

In addition, ROS, as an important mediator of inflammatory response, can cause disorders of endoplasmic reticulum folding protein-related functions, leading to the accumulation of unfolded/ misfolded proteins in the endoplasmic reticulum and the release of Ca2+ in the endoplasmic reticulum into the cytoplasm. High concentration of CA2+ leads to mitochondrial dysfunction and produces more ROS [131]. Due to the long-term existence of this feedback mechanism in the body, intracellular ROS is continuously generated and accumulated, and abnormally accumulated ROS can aggravate endoplasmic reticulum stress.

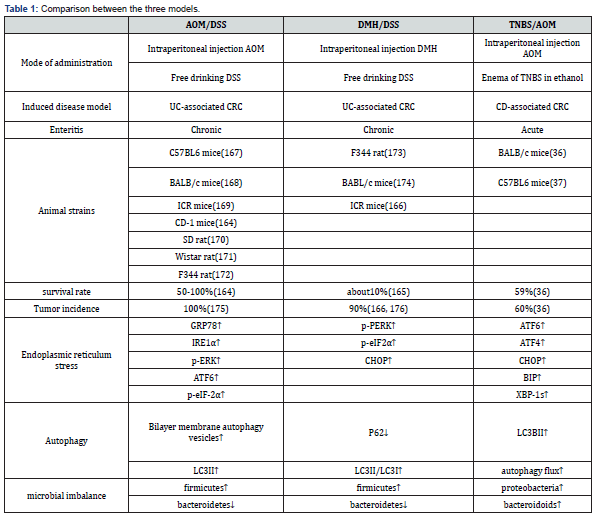
Endoplasmic is the main site for protein folding and quality control. Any disturbance that alters endoplasmic reticulum stress homeostasis may lead to the accumulation of misfolded proteins, the activation of unfolded protein response, autophagy, or apoptosis [132] (Figure 9). Zhang et al. [133] . treated mice with AOM/DSS and found that the endoplasmic reticulum lumen was enlarged, with swelling, vacuoles, and a significant reduction in ribosomes. When the endoplasmic reticulum integrity was destroyed, the expression of GRP78, IRE1α, p-ERK, ATF6 and p-eIF-2α related to endoplasmic reticulum stress was significantly enhanced. Similarly, in TNBS -induced rats [134], the expression of endoplasmic reticulum stress-related proteins ATF6, ATF4, CHOP, BIP and XBP-1s was enhanced. Sharma et al.confirmed that the increased expression of p-PERK, p-eIF2α and chop proteins in rats [135], induced by DMH can lead to endoplasmic reticulum stress.
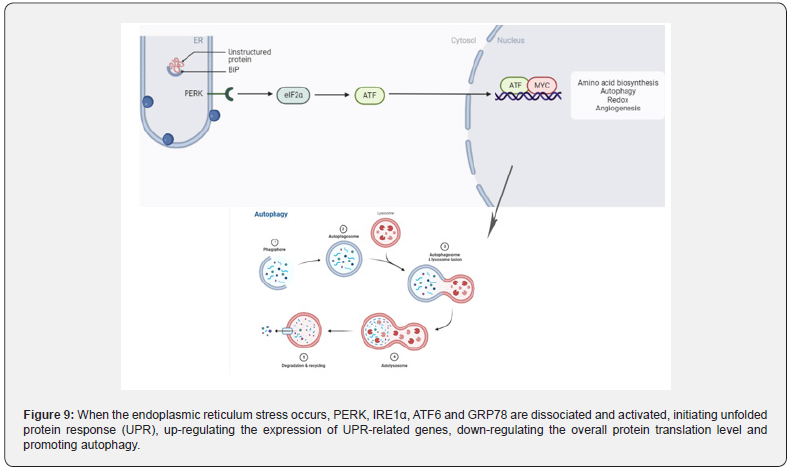
From the mechanism of action, studies have found that IBD-related endoplasmic reticulum stress was associated with autophagy dysfunction [136,137]. Autophagy is a conserved process in eukaryotic evolution through which cytoplasmic materials are degraded in lysosomes [138]. Zhang et al. [133] found that AOM combined with DSS could induce endoplasmic reticulum stress in the intestine of mice and observed a large number of double layers autophagic vesicles in the intestinal epithelial mucosal cells of mice by electron microscopy [138]. The expression of LC3II, an autophagy marker, was also significantly increased. In the DMH/DSS model mice [139]. the expression of P62 and the ratio of LC3II/LC3I were decreased. In TNBS model mice [140], the expression of autophagy related LC3II and autophagy flux were enhanced, and the autophagy ability of intestinal epithelial cells was enhanced.

When endoplasmic reticulum stress occurs in the body, autophagy function is activated [141], which in turn destroys the intestinal mucosal barrier and affects the physiological function of normal intestinal epithelial cells. Subsequently, the diversity of intestinal flora decreased, flora dysfunction [142]. and inflammatory cell infiltration [143] induced IBD, then developed into CAC. AOM/DSS, DMH/DSS and TNBS/AOM can well induce autophagy and endoplasmic reticulum stress during the progression of IBD to CAC.

Intestinal microbial imbalance

The intestinal epithelium is a monolayer of cells that serves as a physical barrier separating the mucosal immune system from symbiotic and pathogenic microorganisms [144]. Epithelial damage or increased epithelial permeability can destroy this barrier, thereby activating the mucosal immune system. Increased intestinal permeability is observed in patients with Crohn ‘s disease before clinical onset or recurrence, suggesting that barrier dysfunction may trigger disease progression [122,145]. The mechanism of IBD caused by intestinal flora imbalance is mainly divided into the following three aspects: the increased number of pathogenic bacteria, the decreased number of probiotics, and the imbalance of flora to break the normal immune tolerance of the body.

At present, the common human pathogenic bacteria are mostly found in Proteobacteria, and the bacteria belonging to Proteobacteria play an important role in the occurrence and development of IBD, especially Escherichia coli. When the intestinal flora is out of balance, the number of mutual pathogenic bacteria increases (such as adhesive invasive Escherichia coli, etc.). Pathogenic bacteria can destroy the normal internal mechanical barrier and immune barrier through invasion and secretion of toxins, increase the permeability of intestinal mucosa, and create conditions for the shift of flora. On the other hand, transferred bacteria over activate the immune response, causing indirect tissues to be attacked and damaged by the immune system [146]. which further increases the intestinal inflammatory response.

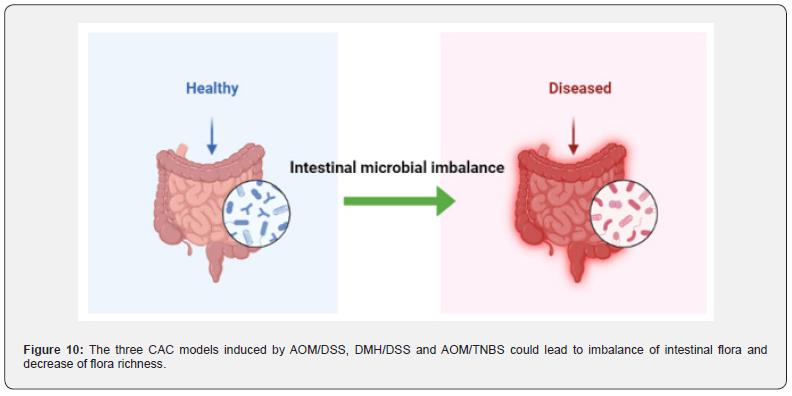
Relevant studies have found that the intestinal mucosal permeability of CD patients is significantly higher than that of normal people, resulting in a large number of bacteria and toxins in the intestine entering the intestinal mucosa and activating immune cells, which will trigger a strong immune response and destroy the mucosa [147]. This may be related to a series of reactions caused by the increase in the number of pathogenic bacteria in CD patients (Figure 9).

There are abundant probiotics in human body, such as Lactobacillus in Firmicutes, Bifidobacterium in Actinobacteria and Bacteroides in Bacteroidetes. When the intestinal flora is imbalanced, the number and richness of Firmicutes and Bacteroidetes in the normal body are reduced, and the number of probiotics such as Lactobacillus and Bifidobacterium is significantly reduced. The above functions are weakened, resulting in impaired intestinal mucosal barrier and proliferation and translocation of pathogenic bacteria. Studies have shown that the bacterial genus in the built-in bacteria can activate Paneth cells to secrete antimicrobial peptides to produce normal antibacterial effects. When the disease causes a significant increase in pathogenic bacteria and a decrease in bacterial genus, the production of antimicrobial peptides is reduced, which further causes excessive immune activation and damage to the intestinal mucosa [148].

Physiologically, there is a symbiotic relationship between intestinal microorganisms and hosts, which depends on a variety of immune mechanisms, such as intestinal mucus secreting immunoglobulin IgA and releasing antimicrobial peptides [149]. In IBD patients, the intestinal microecology is not regulated, and the imbalance of intestinal flora increases the expression and release of inflammatory factors. The normal immune balance of the intestine is broken [150], and the abnormal immune response is activated, resulting in intestinal mucosa and tissue damage.

In AOM/DSS [151] and DMH/DSS [152] treated model animals, the abundance of Firmicutes increased and the abundance of Bacteroidetes decreased, resulting in a decrease in microbial diversity in vivo. In TNBS-induced model animals [153], the intestinal flora composition, species richness and diversity of the model group were significantly different from those of the control group, and the Proteobacteria and Bacteroidetes were significantly increased. After transplantation of fecal microbiota (FMT) in mice, the abundance of these two floras returned to normal levels and microbial diversity increased significantly by observing Shannon curve, PD forest index and CHAO1 index [154] (Figure 10).
Comparison of Three Animal Models (Table 1)

Advantage and disadvantage

AOM/DSS is the most widely used chemical reagent among the three models [155]. It is easy to use, easy to operate, and has a high tumor formation rate that can target tumor formation in animal colorectal regions. At the same time, it has the histological order change of ‘inflammation-dysplasia-carcinoma’. However, there are still some shortcomings in this model. For example, there is a lack of research on cancer stem cells in this model, and the mutations of tumor suppressor genes APC and P53 are rarely seen [156]. CRC has a low tendency of distant metastasis, and the life span of mice is shortened after illness, so it is not suitable for tumor invasion related research [28].
DMH/DSS-induced colon tumors in rodents are very close to human colon cancer in morphology, growth pattern and clinical manifestations [157]. And DMH-induced colorectal adenocarcinoma in mice often invades the submucosa and muscular layer, while AOM-induced colorectal adenocarcinoma does not exhibit such biological and histological properties [158]. However, the main disadvantage of the model using DMH is that multiple injections of DMH and long experimental periods are required to induce colon tumors in experimental animals. Secondly, after DMH is injected into the body, there are many uncontrollable factors in the process of producing AOM by oxidation, and its feasibility is not as high as AOM.

TNBS/AOM, in the construction process, due to TNBS is a semi-antigenic substance, it needs to be combined with ethanol to form a complete antigen, so some researchers use rectal perfusion construction. This model is based on the increased membrane permeability that occurs in IBD, which contributes to the entry of the luminal antigen that immune system cannot fully eliminate, namely haptenization [159]. The main advantages of the model include simple and low-cost protocol and repeatable colonic injury, short duration of the experiment, persistent injury and ulcers with inflammatory cell infiltration. Because of the lack of practice of this technique, the presence of feces in the colon, the anatomical localization of the descending colon, and the volume of the injection rate administered may cause rectal reflux of TNBS, leading to defects in the induction method or increased variability in animal disease.

Pathology

Clinically, IBD patients are also divided into UC and CD. According to Lin et al. [160], UC patients typically present with abdominal pain, increased frequency of diarrhea, and bloody mucopurulent diarrhea. Radiological examination showed obvious edema and hemorrhage of colonic mucosa, diffuse thickening of intestinal wall, occasional cryptitis and deformation of crypt dissection. In CD patients, intestinal wall thickening often occurred in the ileum [161], mucosal thickening and adjacent mesenteric fluid with severe submucosal fibrosis [162]. Saade C et al. [163] reported that approximately 91% of CD patients develop an inflammatory response in the ileum.

In the AOM/DSS-induced mouse UC model, Zhang et al. [133] found that the mice in the model group had pathological symptoms such as diarrhea, vertical hair and anal prolapse, and bloody stools appeared on the 6th day of modeling. Adenoma was diagnosed by histological examination. In Li ‘s experiment, mice in the AOM/ DSS treatment group showed glandular structure disorder and inflammatory cell infiltration. In addition, researchers found that about 80% of mice [164] in the AOM/DSS model group developed adenocarcinoma. In DMH/DSS-induced mice, polyploid adenomatous hyperplasia with malignant transformation of colon, polypoid adenoma [165], thickening of intestinal mucosa, inflammatory cell infiltration [83] bloody stool and rectal prolapse [166].

In TNBS/AOM-treated mice [167], lesions occurred mostly in the distal colon, with colonic crypt abnormalities, accompanied by colorless or polypoidal adenomas, and eventually adenocarcinoma [36]. In addition, some scholars found that AOM/TNBS-induced mice often appear diarrhea [168], bloody stools, colonic mucosal ulcers, submucosal edema and other obvious symptoms of enteritis [37]. Broadly speaking, UC and CD patients will first appear in the body’ s clinical inflammatory response, and then accompanied by abnormal growth of the crypt. However [169], in the three models of AOM/DSS, DMH/DSS and TNBS/AOM, the atypical hyperplasia of intestinal crypt usually appears first, followed by inflammatory cell infiltration and high expression of proinflammatory factors [170].

Conclusion

Various available animal models provide important tools for studying the complex development and pathogenesis of diseases [171]. These models could be used to provide new insights into etiology [172], pathophysiological mechanisms and treatment of human cancers [173]. For example, animal models help us understand the sequential acquisition of genetic and epigenetic changes observed in humans, and the consequent changes in cell behavior and tumor biology [3,159]. Many models are also provided to show the transfer process and the sensitivity to treatment characteristics [174].

Animal studies cannot replace human clinical trials [175], but they must be used in preclinical studies in time so that human diagnosis and treatment-oriented trials can become more concentrated and have a greater chance of success [176]. In fact, these models are not only valuable tools to reveal new mechanisms of CAC pathophysiology [177], but also promising tools to advance our understanding of tumor responses to novel chemoprevention and treatment strategies [178].

Among the three models, AOM/DSS animal model is the most widely used [179,180] the most in-depth studied and the most reductive chemical reagent, which can well simulate the pathogenesis of IBD to CAC [181]. Its operation is simple and convenient [28, 30,182,183] and the success rate and tumor formation rate are higher than the other two modeling methods, and the mechanism of AOM/DSS in vivo is relatively clearer than the other two chemical reagents. Therefore, most of the animal models used for the IBD to CAC process are mainly AOM/DSS [28].

However, the process from IBD to CAC is a complex pathological process induced by multiple factors. Although the model of AOM/DSS-induced IBD to CAC is relatively mature, the effects of diet and environmental factors on the pathogenesis are still not involved [184]. Secondly, the occurrence of cancer is inevitably accompanied by the process of tumor metastasis, but this feature has not been found in AOM/DSS-induced model animals. Thirdly, like any model, the CAC animal model induced by AOM/DSS has its limitations. For example, Kras or p53 mutations are typical in humans, but have not been detected in this mouse model [185]. In contrast, Kras mutations have been observed in CAC rats model using AOM reagent alone [186,187]. In addition, few literatures have compared the pathological features of AOM/DSS, DMH/DSS and TNBS/AOM with clinical related diseases.

If the future technology can combine dietary and environmental factors with the three models of CAC, the clinical tumor metastasis will be modeled in animals, and the clinicopathological features will be compared with the pathological features in the pathogenesis of model animals. It is believed that the pathogenesis of IBD to CAC induced by these three models will be closer to the process of human IBD to CAC, and its pathogenesis will be more comprehensive, providing more reasonable treatment for such patients in the direction of clinical treatment.

To Know more about  Advanced Research in Gastroenterology & Hepatology

To Know more about our Juniper Publishers

Monday, October 16, 2023

Stress Among College Students is Linked to Headache, PCOS, Hypertension, and Depression: A Cross-Sectional Study - Juniper Publishers

 Psychology and Behavioral Science - Juniper Publishers


Abstract

Objective: In the present study, we aimed to find out the prevalence of stress among college students.

Methods: In this descriptive cross-sectional study, a simple random sampling approach was chosen for data collection from different colleges of Jammu & Kashmir (UT). Data analysis was done by using the chi-square test, and the t-test was utilized for discrete and continuous variables respectively. The logistic regression model using odds ratio was utilized to find out the association between the risk variable and the dependent variable.

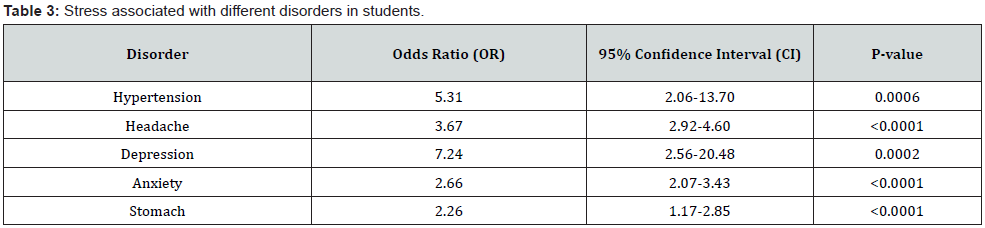
Results: A total of 1405 college students were included in which stress was found in 60.49% of students with males representing 34% and females 65.88%. Educational stress was found to be the major contributor of stress-type faced by the students with 46.35%. Different disorders were also observed in students including hypertension 2.70%, PCOS (Poly-cystic ovarian syndrome) 2.34%, and depression 2.84%. Stress was found associated with the PCOS with OR: 3.62 [95% CI: 1.4850-8.84, p-value: 0.0047], headache OR: 3.67, hypertension OR: 5.31 [95% CI: 2.06-13.70, p-value: 0.0006] and depression OR: 7.24 [95% CI: 2.56-20.48, p-value: 0.0002].

Conclusion: Educational stress is found to be very common among college students which may alter the prosperous life of students. Female students were seen to be more stressed than male students. Stress has a strong detrimental impact on students’ health because it is considerably linked to conditions including hypertension, PCOS, and depression. Therefore, the educational system must need a better strategy that will ensure a better education system.

Keywords: Stress; Educational stress; Hypertension; PCOS; College students

Abbreviations: PCOS: Poly-cystic ovarian syndrome; SAA): Salivary Amylase Activity; FGD: Functional Gastrointestinal Disorders; IBD: Inflammatory Bowel Disease; PU: Peptic Ulcer; UC: Ulcerative Colitis; CRH: Corticotrophin Releasing Hormone; ACTH: Adrenocorticotropic hormone; OR: Odds Ratio; OECD: Organization for Economic Co-operation and Development

Introduction

In today’s world, many shortcomings need to be eliminated and education is the one that is often seen as a solution to many social problems. Education is an important instrument that has the power to make a person interactive, self-reliant, social, and disciplined. Education broadens the scope of learning by facilitating knowledge absorption and dissemination among people in order to advance society [1]. Every individual is bombarded with a multitude of perceptual information in their day-to-day life activities. Apart from such advantageous features of education, the ability to process information is limited and varies from person to person. These cognitive characteristics have the potential to disrupt students’ lives periodically, which might result in circumstances that resemble stress and anxietylike condition. According to physiological definition, stress may be described as “any form of change that results in bodily, emotional, or psychological strain or pressure”.

It could result from a traumatic, disappointment, or uneasy encounter or sensation [2]. It is not that stress is bad, “Eustress” describes stress as a “positive, motivating, and enhances functioning feature which leads to the excellent performance” while “distress” refers to bad and overwhelming stress full condition which leads to tiredness, despair, and a variety of other illnesses and thus impairs functioning [3]. Albeit intense or transient pressure can be helpful but ongoing pressure, which goes and remains for a more extended period, is very unfavorable to the body and causes hypertension, weight gain, sadness, and even coronary diseases [4]. The effects of anxiety on students’ academic performance were detrimental [5] and besides anxiety, another emotionally uncomfortable disorder that could interfere with a student’s life is depression.

Stress affects students’ life in a variety of ways, including how they perform academically, socially, physically, and emotionally [6]. Exam stress, a lack of interest in attending lectures, full schedules &responsibilities, lack of sleep, an inability to understand the topic, and academic pressure (pressure to achieve high marks and concerns about receiving poor grades) are some examples of stresses faced by students [7]. The cognitive system becomes overburdened under stressful settings, reducing the student’s attention and ability to process the perceived information [8]. Biologically, stress can lead to long-term health complications, chronic illness, and psychiatric conditions such as migraine, PCOS (poly Cystic Ovarian Syndrome), depression, and suicide [9-11].

The Organization for Economic Co-operation and Development (OECD) recently conducted a survey that included 540,000 students aged 15-16 years old from 72 nations which showed that education and academic achievement are major sources of stress for students [5]. Therefore, in the present study, we aim to find out the stress frequency among college students of Jammu division. To our knowledge, this is the first study that included 10 district colleges from our region. The remainder of the paper is laid out as follows: methods utilized in this study are depicted in Section 2, section 3 includes the result of the study, section 4 represents the discussion and the conclusion of the study is present in section 5.

Method

In this present descriptive cross-sectional study, a random sampling approach was chosen for data collection from different colleges in the Jammu division of Jammu & Kashmir (UT). The sample collection was done in two phases i.e., Phase-I (Face-face interview) and Phase-II (E-based sampling).

Sample Collection

A targeted survey was taken in the colleges of the Jammu division to gather data from the different college students. The information was gathered using two different phases, including face-to-face interviews (Phase-I) conducted by an experienced interviewer/ trained interviewer and online sampling/ E-Sampling using a google form (Phase-II). The questionnaire/ Google form was disseminated through emails and social networking sites. The present study design was duly approved by Animal and Human Experimentation Ethical Committee (AHEEC), University of Jammu vide notification number EC: DRS/22/4969.

Filtering and Data Cleaning

A large data set was obtained using the E-based sampling approach, and the data was cleaned and filtered using a variety of exclusion criteria to decrease redundancy and bias. Exclusion criteria include “students that did not belong from the district of Jammu division”, “non-college students”, “who don’t permit for use of their data (incomplete consent)”, and also the exclusion of subject data “who gave the partial information”.

Data analysis and statistics

For the descriptive data analysis, mean with Standard deviation and frequency distribution were used for the continuous and discrete variables respectively. The chi-square test and the t-test were utilized for the discrete and continuous variables, respectively, in the inferential statistics. The logistic regression model utilizing the odds ratio (OR) was used to determine whether the risk variable and the dependent variable i.e., diseases were associated or not. Online free statistical tools/calculators such as MedCalc’s Odds ratio calculator for calculation of Odds ratio, t-test were calculated by graph-pad Home-GraphPad and for chi-square statistics Social Science Statistics (socscistatistics.com) were used to draw out the inference.

Result

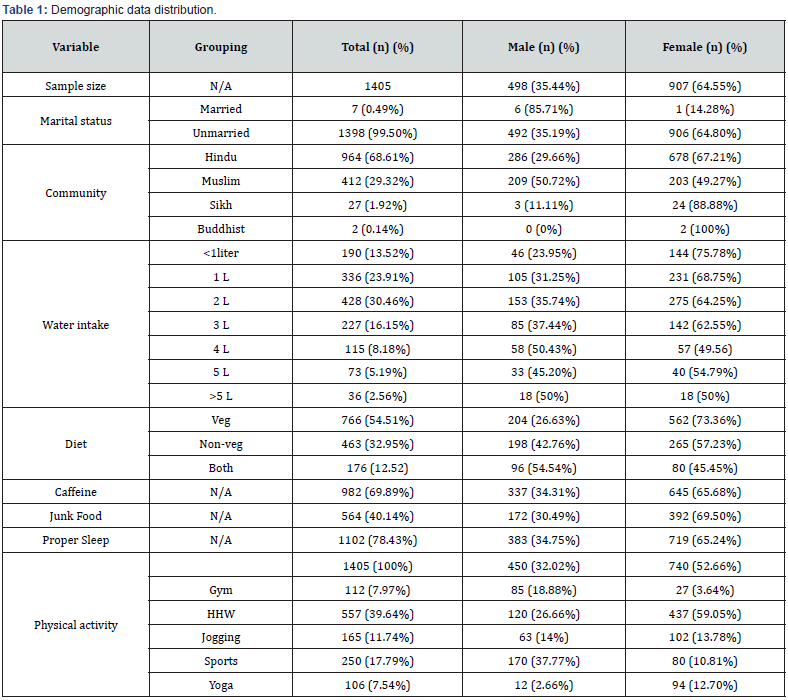
A total of 1405 college students were included with a mean age of 19.64±1.32, including 498 males (19.46±1.32) and 907 females (19.74±1.31). We found a highly statistical difference between the age of male and female students among college students (t-test: 3.8220: p-value: 0.0001). The majority of students were belonging to the Hindu community (n=964) in contrast to Muslims (n=412) and with minorities including Sikhs and Buddhists n=27 and n=2 respectively (Table 1) (Figure 2A). Regarding the martial estimates, the frequency of married students was not quite high (0.49%) (Table 1). Lifestyle activity of students has been also observed where it is found the lower frequency of alcohol usage 1.35% (n=19/1405) in which the male participants represent the dominancy 72.68% (n=14/19) over the female 26.31% (n=5/19).

Also, the increased smoking habit was observed in males 71.42% (n=15/21) in contrast to female students 28.57% (n=6/21). Around 1190 students (84.69%) were observed to do physical activities including n=450 males (37.81%) and n=740 female (62.18%) (Figure 2E) (Table 1). Regarding the dietary pattern, it was observed that 32.95% (n=463) were non-vegetarian (n=766) were vegetarian and 12.52% (n=176) take both (veg % and non veg.) and with respect to the caffeine 69.89% (n=982) were taken caffeine out of which32.29% (n=327) were occasional (Figure 2B) (Table 1). Stress was found in 60.49% students (n=850/1405) with the male representing 34% (n=290/850) and female 65.88% (n=560/850). We observed statistically significant difference (t-test = 3.3926, p-value: 0.0007) between the age difference between stressed males (19.46±1.33) and females (19.78±1.29).

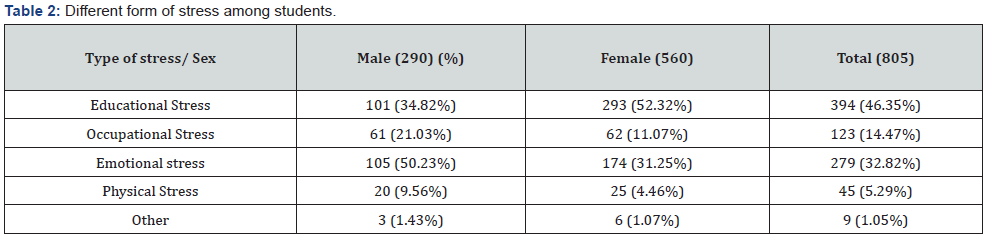
The frequency of the different types of stress was observed (Table 2) and the educational stress was at the top representing 46.35% including 34.82% (n=101/290) and females 52.32% (n=293/560) (Figure 2F). Different disorders were observed in students which include hypertension 2.70% (n=38/1405), PCOS (Poly-cystic ovarian syndrome) 2.34% (n=33/1405), and depression 2.84% (n=40/1045). To find out the risk attribute associated the condition Odds ratio (OR) were utilized. Stress was found associated with the headache OR: 3.67,95% CI: 2.92-4.60, (p value: <0.0001), PCOS with OR: 3.62 [95% CI: 1.4850-8.84, p-value: 0.0047], hypertension OR: 5.31 [95% CI: 2.06-13.70, p-value: 0.0006] and depression OR: 7.24 [95% CI: 2.56-20.48, p-value: 0.0002]. Also, caffeine risk on hypertension and PCOS were also observed including OR: 5.24 [95% CI: 1.60-17.17, p-value: 0.0061] and OR: 3.12 [95% CI: 1.13-9.34, p-value: 0.027] respectively.

We also observed the bidirectional association of headache and hypertension and found a significant increase of risk i.e., headache to hypertension OR: 14.65, 95% CI: [6.59-32.57], (p-value: 0.0001) and hypertension to headache OR: 3.61, 95% CI: [1.64-7.94] (p-value: 0.0014). Stress was also found significantly (p value <0.0001) associated with the risk of anxiety (OR: 2.66, 95% CI: [2.07-3.43] and risk of stomachache (OR: 2.26, 95% CI: [1.17-2.85]) (Table 3). Educational stress was found significant (p value: <0.0001) responsible for increasing the likely hood of headache by 3.8-fold (OR:3.84, 95% CI: 2.92-5.05). Emotional stress was found to be a high-risk variable associated with hypertension with an OR: 2.74 [95% CI: 1.35-5.54, p-value: 0.0050]. Also, the association between emotional stress and PCOS was observed with an OR: 1.14 [95% CI: 0.50-2.58] but did not reach at statistical significance (p-value: 0.74).

Discussion

Education has a crucial role in society since it may influence people’s attitudes, ways of thinking, and behaviors [12]. But stress which is an inevitable part of life has a detrimental effect on student’s physical and emotional health as well as their academic performance. In the present study, we observed that college female students were more stressed than the male participants, with the female group showing higher levels of educational stress (Figure 3F). Also, emotional stress was found to be more frequent in the female group as compared to the male students (Figure 3F). College students experience stress due to increased workload, new responsibilities, poor time management, and interpersonal relationships [13].

In comparison to our study, many research studies have provided significant data on stress and students and their relationship. According to Waghachavare and colleagues, 25.1% of medical students, 28.7% of dentistry students, and 19.7% of engineering students reported feeling stressed out. In comparison to the gender disparity, female students were found to be more stressed than the male participants [14-16]. According to published data, secondary school students had a medium degree of tension, with females being shown to be more stressed [17]. In the college institution, more than one-fifth of college students suffer from mental problems [18] and the academic domain was the most common source of stress, followed by the social activity area, and group activity domain [19]. Regarding the academic domains, science, and commerce domains students were shown to be more academically stressed than the students in the arts, management stream, and humanities [20]. The fact is that most of the female respondents feel stress in their college life because of fear of failure [21,22].

Reasons for the stress among the students were found the lack of appropriate support, a variety of personal and social issues, academic pressure, extracurricular activities, assignments overburden, and most importantly parents want their children to participate in the rat race and outperform their peers to improve their social status, the attitude of faculty members [16,23,24]. Rana and colleagues reviewed that stress can be either bad or positive for a person, depending on the severity and duration of the stress, the person’s personality, cognitive assessment of the stress, and social support. They must be raised in a positive environment and more attention is paid to the child’s growth as they enter adolescence [7]. Extreme stress can make it difficult to work effectively, as well as cause poor academic achievement and reported poor health and a lower quality of life [13] and there was no association between high-stress levels and students’ age [15].

The biological aspect of stress is complicated where stress has much negative feedback. One such example is the stress-induced stimulation of the hypothalamus to secrete CRH (Corticotrophin releasing hormone) which then further stimulates the anterior part of the pituitary gland to release ACTH (Adrenocorticotropic hormone) [25]. ACTH flows down from the brain to the kidney through the bloodstream (endocrine signaling) and binds to the specific receptor on the Adrenal gland (located on the kidney) and stimulus to secrete the adrenaline and cortisol. Adrenaline and cortisol alter the homeostatic mechanism of the different systems including heart rate, dilation of bronchioles, increasing blood pressure, increasing blood glucose level by converting glycogen, and decreasing digestive activity (Figure 4). Long-term and continuous stimulus results in a dysregulated mechanism which leads to different diseases such as heart diseases [26], asthma [27], Obesity, Diabetes [28], headaches including migraine [11], depression [29] and anxiety [30], gastrointestinal problems [31], Alzheimer’s disease [32] etc. (Figure 5).

In the present study, we have observed that stress negatively impacted the reproductive health of females where it significantly increases the chance of PCOS (Poly-cystic Ovarian Syndrome) OR: 3.62 [95% CI: 1.4850-8.84, p-value: 0.0047]. Also, structural changes in blood vessels i.e., hypertension found to be significantly associated with stress with OR: 5.31 [95% CI: 2.06- 13.70, p-value: 0.0006]. Mental status among students is the seed for progress but stress has created a distressing environment for the brain and alters its normal activity. We have also observed that stress increases 7 times more chance of depression among students with OR: 7.24 [95% CI: 2.56-20.48, p-value: 0.0002]. Emotional stress was found to be a high-risk variable associated with hypertension with an OR: 2.74 [95% CI: 1.35-5.54, p-value: 0.0050]. Also, the association between emotional stress and PCOS was observed with an OR: 1.14 [95% CI: 0.50-2.58] but was not reached statistical significance (p-value: 0.74). Students have a lot of stress related to their academics, where we found that educational stress is significantly associated with the increased likelihood of headache (OR:3.84).

PCOS results in low self-esteem which causes the majority of psychiatric conditions, such as depression and suicide [9]. Stressrelated factors such as Salivary Amylase Activity (SAA) and salivary cortisol levels were found to be higher in PCOS patients than in age-matched controls, implying an exaggerated response of the central stress stations in the affected women [33,34]. Early life stress such as abuse, and school bullying play a significant effect on the susceptibility to develop FGD (Functional Gastrointestinal Disorders) and IBD (Inflammatory Bowel Disease) later in life [35], gastrointestinal conditions like peptic ulcer disease (PU) and ulcerative colitis (UC). Psychological stress has been found to negatively impact the immune system which worsens the number of skin and hair conditions like psoriasis, alopecia areata, and atopic dermatitis [36].

Humensky and group have shown that self-reported depressive symptoms were associated with concentration difficulties and difficulty completing school tasks between 14 to 21 aged students in the United States were at risk for major depression [37]. One-fifth of college students had mental problems, indicating that mental health is a serious problem that increases with the children’s grade level [18]. These findings imply that there is a strong link between stress or stress-related factors and altered body composition. Also headache and hypertension has been found to be linked with each other (comorbid conditions) [38,39] and this might be due to the presence of diverse risk attributes such as environmental including stress and genetic factors [40].

To this end, the future of any nation lies in its students, who are blessed with incredible abilities; we simply need to discover them. Despite of advanced learning and teaching approach, enhancement of students is not at its peak. Stress is a major reason for the decreased development of students which negatively impacted their health, social status, future goals, their academic life, and many other important life aspects. Therefore, emphasizing the value of research, improving pupils’ growth may be accomplished by suggesting some coping mechanisms like college students should pay attention to their health and nutrition, take proper sleep, manage their time effectively, practice self-care, make connections with others, maintain healthy relations, focus on physical activities, use relaxation techniques like meditation, live organized life, practice positive thinking etc. All of these will help college students to increase their overall health and can reduce stress. Avoiding stress decreases and increases the likelihood of disease occurrence and happy and healthy existence respectively.

Conclusion

If a healthy solution cannot be found, stress can have a negative influence on academic performance and mental health. Therefore, there must be needed a system that will ensure a better education system. Colleges must develop coping strategies to reduce stress triggers and improve student experiences by identifying the causes of stress (financial struggles, academic pressure, studentteacher relationship, conflict with a roommate, family issues, relationship issues, career problems, post-graduation plans etc.) which disrupts student’s daily activities and how to manage it.

To Know more about  Psychology and Behavioral Science International Journal

To Know more about our Juniper Publishers
Click here: https://juniperpublishers.com/index.php

Friday, October 13, 2023

The use of Biomaterials in Infection Prevention in the Hospital Environment - Juniper Publishers

Biomedical Engineering & Biosciences Journal- Juniper Publishers


Abstract

Biomaterials are increasingly gaining space in the hospital environment because they provide researchers with a broad investigative aspect to compose new strategies for use in clinical practices. In this context, the present study aims to investigate the use of biocompounds with antimicrobial action as an alternative in the coating of surfaces in the hospital context. Thus, the guiding methodology of this study was a narrative review of the literature. To this end, the following databases were consulted: PubMed, Embase, Lilacs, using the PICo strategy and subjected to the following descriptors: (“Biomaterial” OR “Biopolymer” OR “Polymer”;) AND (“Nosocomial infections”) AND (“RCT OR randomized OR random OR case-control”). It was observed in this study a wide use of biomaterials, especially hydrogels related to natural compounds with the purpose of promoting antimicrobial action in the hospital environment, fighting pathogens, especially bacteria and fungi, which are responsible for most hospital infections. Furthermore, the use of copper and chitosan nanoparticles for coating dental and medical materials was verified, with bactericidal activity for the pathogens Staphylococcus aureus and Pseudomonas aeruginosa, affirming that the development of these surfaces is a promising tool against infections acquired in the hospital environment. Thus, the results obtained report a new perspective on combating antimicrobial agents responsible for aggravating patient life in the hospital setting.

Introduction

In the hospital environment, surfaces and objects such as syringes, scissors, catheters are more prone to the development of bacterial contamination, characterizing a potential mode of infection transmission in this environment [1]. Thus, microorganisms commonly acquired in this environment are characterized by presenting resistance to drugs, such as antibiotics and antimicrobial agents, especially strains of Staphylococcus aureus and Pseudomonas aeruginosa, which are the most responsible for the development of bacterial biofilms and transmission of infections [1,2].

Thus, the scarcity of drugs with effective action generates the need for measures that mitigate this problem. At the same time, antimicrobial coatings have presented themselves as a new aspect of research, in order to contribute positively to the progress of science in this field. In this context, biomaterials gain prominence, through sets of synthetic or natural substances, which aim to replace non-functional matter with biocompatibility, accessibility, biodegradability in certain situations [3]. Thus, the applicability of these materials in hospital environments in order to prevent the formation and proliferation of microorganisms is considered [2].

In this prism, it is coherent to emphasize the necessity of involving interaction of the living organism with the biocompounds, besides promoting biocompatibility in possible cases of surgery [4]. A vast number of these products are available on the market. One can mention biomaterials in the composition of intravenous catheters as prevention of phlebitis, such as the use of vialon, which demonstrates a lower rate of inflammation when compared to Teflon catheters. Or even, endotracheal tubes coated with biocompounds, which present themselves as a good proposition in preventing the formation of bacterial biofilms helping to prevent infections, are examples of strategies with good results in the hospital context [5,6]. In this conjuncture, the need to explore and develop research aiming at the promotion and application of these strategies as methods and treatment prophylaxis is exalted, as well as for exposing and reviewing data already available on the theme in the scientific literature. Thus, the study aims to describe the potential of the use of biomaterials in the hospital context aiming at preventing infections in patients.

Methodology

Characterization of the study

A narrative of the scientific literature was conducted as a methodological tool to conduct this study. It is a qualitative and descriptive study, which used the scientific bibliography to expose the theme. Thus, the analysis developed had the purpose of prioritizing the capture of the most relevant data in order to obtain a critical view of the subject.

The conception of the state of the art on the chosen theme occurred from a broad search, subsidized by the protocol mentioned by Almeida et al. [7] The synthesis of this article occurred from the elaboration of the guiding question. For this purpose, the acronym PICO, corresponding to population/ interest/context of the research in question, was used.

Conducting the investigation

The study in question raised the question: “What is the effect of hospital materials coated with biomaterials (P), as an antibiotic therapeutic strategy (I), considering cases of infections developed from the use of these objects (Co)?”. Moreover, the conduction of this investigation began during the months of January until March 2023 in online databases of scientific articles, such as PubMed, Embase, Lilacs. In this bias, descriptors were selected in the following search formula: (“Biomaterial” OR “Biopolymer” OR “Polymer”;) AND (“Nosocomial infections”) AND (“Biofilm” or “Antimicrobial” or “Antibiotic”) AND (“RCT OR randomized OR random OR case-control”). For the success of this review, a time interval of the last 5 years was prioritized, however, there were no restrictions when the relevance of the data was perceived. The chosen studies expose directly in their title and abstract that their research refers to a look directed to the issues of nosocomial infections after the use of medical objects.

Selection parameters

This research selected and prioritized works published as scientific articles, written in the languages: Portuguese, English and Spanish. Soon after the selection of findings, the works that did not meet or were not formulated to answer the central question of this publication were excluded. Thus, the studies approved to compose this article had their most relevant information highlighted in order to contemplate the purpose of the scientific development of this work.

Presentation of the results and synthesis of the information

Thus, after contemplating each paper individually, the review was drafted to match the scope of the investigation. Illustration 1 shows the methodological step followed. It is consistent to point out that submission to the Ethics Committee was not necessary, since the samples are in the public domain (Figure 1).

Results and Discussion

Currently, biocompounds have been gaining space in the biomedical and medical engineering area, because they present satisfactory results in the interaction in systems, such as coating objects, prostheses and implants and treatments of health problems [3]. Thus, the importance of such materials is perceived, because they present themselves as possibilities of innovation aiming to contribute with antimicrobial action against pathogens increasingly resistant to drugs.

That said, throughout the construction of this research, 11 studies were pre-selected, correlating natural or synthetic products with application in the hospital environment. Among these, 7 were correlated to the use of biomaterials in the hospital environment and 4 presented data and studies only on synthetic or natural compounds. After the selection, the chosen works were analyzed in their entirety, highlighting the main data for later achievement of a more critical analysis regarding this issue.

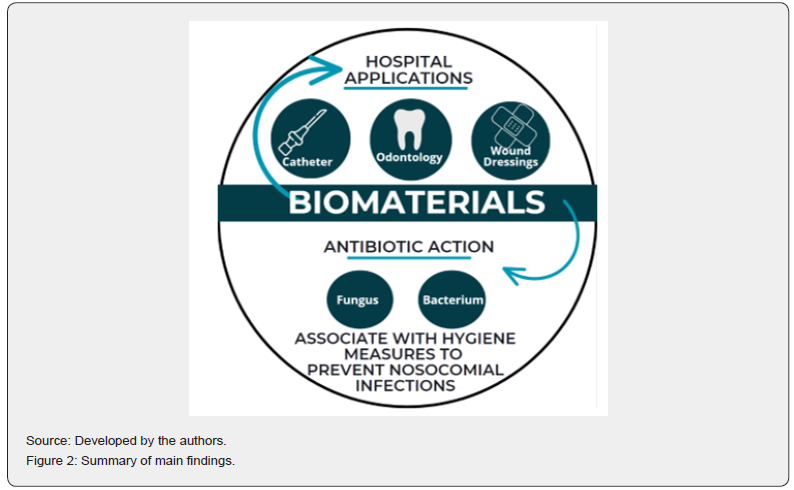
The characteristics of the selected studies were, as to the methodological approach adopted by the authors, literature review, exploratory experimental method, and randomized study. The languages of publication were Portuguese and English, and the publication ranged from the years 2013 to 2021, being selected articles published in journals, as well as thesis results. The synthesis of the main results observed is shown in (Figure 2).

In Heilman’s study [8] a catheter with a polyurethane coating with silver nanoparticles was developed, and it was observed that the use in various polymers, such as polyurethane and silicone, resulted in excellent antimicrobial activity against a broad spectrum of organisms in vitro, such as growth and adhesion of Staphylococcus aureus on the device surface.

Andrade [9] produced a hydrogel combined with chitosan nanoparticles to combat infections and burns infected by bacteria of the genus S. aureus, demonstrating that the compound encapsulated in Nps-H proved to be 2 to 3 times more active than the free compound (C-H) against the tested strains, thus being a possible application of the material in the treatment of infected burns.

Tavaria [10] studied chitosan as a biomaterial for coating dental objects, proving that the antioxidant, antimicrobial, healing power and anti-inflammatory action of this compound, inhibits the proliferation of biofilms potentiating the treatment of diseases associated with the oral cavity, especially Streptococcus mutans. Furthermore, it was observed that applying mouthwashes, toothpastes and dental materials based on chitosan can reduce and prevent the number of microorganisms present and accelerate the healing process.

Assunção [11] investigated copper-based coatings and their influence on the behavior of bacteria, and concluded that copper possesses bactericidal activity for the pathogens Staphylococcus aureus and Pseudomonas aeruginosa, stating that the development of copper surfaces are a promising tool against hospital-acquired infections.

Antezana [12] developed a biomaterial for coating dressings, with long-term antimicrobial effects from collagen directly related to hydrogel and silver nanoparticles against bacteria S. aureus and P. aeruginosa. Such compounds presented satisfactory results against infection caused by such pathogens and proved to be effective in wound healing application.

Gonçalves [13] performed a study testing the oil Melaleuca alternifolia Cheel, evaluating the antifungal activity of this compound against yeasts of the genus Candida spp. responsible for 80% of all hospital fungal infections. It was concluded that, the synthesized material showed a good fungicidal, stable and antioxidant action, revealing itself with great potential to combat these microorganisms.

From this, it is possible to demonstrate that biomaterials in the prevention of hospital infections have scientific support, but do not replace asepsis and sterilization strategies. Thus, it is proposed that a greater application of these compounds with antibiotic, antimicrobial, antioxidant potential and prevention of bacterial biofilm formation occur in the synthesis of such materials, in order to act together with the already recommended hygiene strategies to mitigate the number of infections acquired in these health institutions.

Conclusion

Given the tested and proven action in the most variable studies available in literature, biomaterials are revealed as a new potential alternative in the fight against multidrug-resistant pathogens. It is worth pointing out that these compounds have shown great relevance in several areas, from acting in the development of catheters, dental objects or wound coverings, proving to be a method of great versatility. Furthermore, it is of paramount importance to emphasize their high impact activities against pathogens that cause hospital infections, especially bacteria and fungi. Therefore, this study demonstrated the alternatives to combat the microorganisms that are in the hospital environment causing the worsening of the patient’s health through biomaterials. However, it is clear the need for a greater research framework in this area, such as the development of more clinical studies. It is recommended, therefore, the use of these strategies concomitant to the hygiene conducts present in the hospital environment, to achieve better results in fighting infection.


Thursday, October 12, 2023

Neuropsychiatric Lupus: A Review of Clinical Features and Treatment Strategies - Juniper Publishers

Orthopedics and Rheumatology - Juniper Publishers


Abstract

Neuropsychiatric lupus, also known as neuropsychiatric systemic lupus erythematosus (NPSLE), is a subset of systemic lupus erythematosus (SLE) that affects the central nervous system, leading to a range of neurological and psychiatric symptoms. It occurs in approximately 25-75% of SLE patients, varying prevalence across populations. NPSLE primarily affects women of childbearing age but can occur in individuals of any age or gender, with a higher prevalence among non-Caucasian populations and those with severe SLE symptoms. The exact cause of NPSLE is complex, involving immune dysregulation, autoantibody production, and central nervous system inflammation. Autoantibodies, such as anti-phospholipid and anti-NMDA receptor antibodies, may significantly affect neurological symptoms. Immune-complex deposition and proinflammatory cytokines within the brain contribute to the disease’s pathophysiology. NPSLE encompasses many symptoms, including cognitive impairment, mood disorders, psychosis, seizures, and headaches. Diagnosis relies on clinical evaluation, neuroimaging, cerebrospinal fluid analysis, and autoantibody testing. A multidisciplinary approach involving rheumatologists, neurologists, and psychiatrists is often necessary. Treatment for NPSLE is tailored to the specific symptoms and their severity. It typically involves immunosuppressive therapies like corticosteroids, disease-modifying antirheumatic drugs (DMARDs), and sometimes biological agents. Adjunctive therapies, including antiepileptic drugs, antipsychotics, and antidepressants, may be necessary for symptom management. Regular monitoring and follow-up are crucial to assess treatment response.

The article discusses the epidemiology of SLE and NPSLE, emphasizing the variability in prevalence across different populations. It highlights the challenges in diagnosing NPSLE due to its diverse and often nonspecific symptoms. Various diagnostic criteria and biomarkers are discussed, emphasizing the need for a personalized diagnostic approach. The article also covers the differential diagnosis of NPSLE, distinguishing it from other autoimmune diseases, infections, and medication-induced symptoms. Regarding prognosis, NPSLE is associated with a poorer quality of life and increased mortality compared to SLE without neuropsychiatric involvement. Specific factors, such as anti-ribosomal P antibodies and acute confusional states, are linked to worse outcomes. Mortality in NPSLE is often due to infections.

Neuropsychiatric lupus is a complex condition characterized by neurological and psychiatric symptoms. Early diagnosis and multidisciplinary management are essential to improve outcomes and the quality of life for patients with NPSLE. Further research is needed to understand its pathogenesis and improve diagnostic and treatment strategies.

Keywords: Neuropsychiatric Lupus; Systemic Lupus Erythematosus; Neuropsychiatric Systemic Lupus Erythematosus; Immune Dysregulation; Central Nervous System; Immune-complex deposition

Abbreviations: NPSLE: Neuropsychiatric Systemic Lupus Erythematosus; SLE: Systemic Lupus Erythematosus; CNS: Central Nervous System; DMARDs: Disease-Modifying Antirheumatic Drugs; IVIG: Intravenous Immunoglobulin; MRI: Magnetic Resonance Imaging; CSF: Cerebrospinal Fluid; MS: Multiple Sclerosis; APS: Antiphospholipid Syndrome; EULAR: European League Against Rheumatism; SLICC: Systemic Lupus International Collaborating Clinics

Introduction

Neuropsychiatric lupus, also known as neuropsychiatric systemic lupus erythematosus (NPSLE), is a subset of systemic lupus erythematosus (SLE) characterized by the involvement of the central nervous system. It encompasses a spectrum of neuropsychiatric symptoms and manifestations that can significantly impact a patient’s quality of life. NPSLE is relatively uncommon, occurring in approximately 25-75% of SLE patients, with variations depending on the population studied and the diagnostic criteria applied [1,2]. The disease predominantly affects women of childbearing age but can occur in individuals of any age or gender. The prevalence of NPSLE is higher among non-Caucasian populations and those with more severe SLE manifestations. The exact pathogenesis of NPSLE remains complex and multifactorial, involving immune dysregulation, autoantibody production, and inflammation within the central nervous system. Autoantibodies, such as anti-phospholipid, anti-NMDA receptor, and anti-ribosomal P antibodies, may play a pivotal role in developing neurological symptoms. Immune-complex deposition and proinflammatory cytokines within the brain parenchyma contribute to the pathophysiology of NPSLE [1-3].

NPSLE encompasses neurological and psychiatric symptoms, including cognitive impairment, mood disorders (e.g., depression, anxiety), psychosis, seizures, and headaches. Patients may present with focal neurological deficits, aseptic meningitis, or cerebrovascular events. Symptoms can be episodic and fluctuate, making diagnosis and management challenging [1,4]. The diagnosis of NPSLE is primarily clinical and relies on a combination of neurological and psychiatric assessments, neuroimaging studies, cerebrospinal fluid analysis, and excluding other possible causes of neuropsychiatric symptoms. Autoantibody testing, such as anti-dsDNA and anti-cardiolipin antibodies, can aid in diagnosis. A multidisciplinary approach involving rheumatologists, neurologists, and psychiatrists is often necessary for a comprehensive evaluation [5].

The management of NPSLE requires a tailored approach based on the specific neurological or psychiatric manifestations and their severity. Treatment typically involves immunosuppressive therapies, including corticosteroids, disease-modifying antirheumatic drugs (DMARDs), and, in some cases, biological agents. Adjunctive therapies such as antiepileptic drugs, antipsychotics, and antidepressants may be necessary to control specific symptoms. Regular monitoring and follow-up are essential to assess treatment response and adjust therapies as needed [3,6]. This narrative review aims to provide an overview of neuropsychiatric lupus’s clinical features and treatment strategies. Despite the complexity of this condition, early diagnosis and multidisciplinary management can help improve outcomes and the quality of life for patients with NPSLE.

Epidemiology

Patients diagnosed with systemic lupus erythematosus (SLE) may experience neuropsychiatric clinical manifestations due to abnormalities affecting the central, peripheral, and autonomic nervous systems. Considerable heterogeneity exists in the published estimates of SLE occurrence, even when examining data from within a single country or geographical area [7]. The available evidence from cohorts of patients diagnosed with SLE indicates that approximately 50% of these individuals will experience neuropsychiatric manifestations of the disease at some point during their illness [8]. A comprehensive analysis of several studies completed worldwide over the past 15 years shows that SLE’s prevalence varies between 9 and 241 cases per 100,000 person-years [7]. Similarly, the incidence of SLE ranges from 0.3 to 23.2 cases per 100,000 person-years. The observed variance may be attributable to genetic variation and exposure to environmental factors [7].

The American College of Rheumatology (ACR) categorization criteria for neuropsychiatric systemic lupus erythematosus (NPSLE) have gained significant acceptance in clinical research about NPSLE. Recent studies imply that SLE is responsible for 30 - 50% of all NP episodes in SLE patients, while the actual amount differs based on the type of NP event [8]. Some studies utilizing ACR criteria estimated the prevalence of NPSLE to be between 37% and 95%, though 90% of the estimate is pure CNS manifestations [7-9]. The prevalence of neuropsychiatric systemic lupus erythematosus (NPSLE) is estimated to be approximately 50 in 500,000 in the United States [8,9]. However, this statistic is challenging due to numerous study designs. The clinical manifestations of SLE can range from minor or organ-restricted disease to full-blown life-threatening illness. The most noted presentations of NPSLE were headache, mood disorders, cognitive dysfunction, seizures, cerebrovascular disease, and other minor nonspecific central nervous system (CNS) symptoms [7-9].

Pathogenesis

Two pathways have been proposed: an autoimmune or inflammatory pathway that causes damage to the bloodbrain barrier through the deposition of unclean complexes and inflammatory mediators. And the ischemic route through thrombosis that causes cerebral microangiopathy. Autoantibodies are considered a possible culprit in the pathogenesis of NPSLE [10].

The mechanisms by which inflammation contributes to neuropsychiatric symptoms are unclear. Some lupus autoantibodies cross-react with the N-methyl-D-aspartate (NMDA) receptor, a brain glutamate receptor. These antibodies are increased in acute confusional states in lupus, but there are no clear correlations between can cause mood alterations and fatigue and autoantibodies in SLE [11]. Most cerebrovascular disorders in NeuroPsychiatric Lupus (NPSLE) are due to antiphospholipid antibodies (aPL) associated with developing thrombosis. In addition, aPL has been reported to be associated with headaches, chorea, transverse myelitis, and epileptic seizures [12,13]. Anti- DNA/NR2 and anti-ribosomal P antibodies are considered to target specific parenchymal structures in the brain and underlie the onset of NP manifestations. Anti-Sm antibodies (anti-Sm) and anti-U1-ribonucleoprotein antibodies (anti-RNP) are frequently found in patients with NPSLE. In addition, anti-aquaporin 4 antibodies (anti-AQP4), diagnostic markers for neuromyelitis optica spectrum disorder (NMOSD), contribute to NPSLE [14].

Experimental studies in humans show that inflammatory cytokines released by the immune system can cause mood disorders and fatigue, and animal studies show that these cytokines can alter behavior by acting directly on the brain and brain endothelium. However, it is unclear to what extent immune activation and cytokine release contribute to altered mood and fatigue in SLE [15].

Clinical Features

Neuropsychiatric manifestation of systemic lupus erythematosus (NPSLE) is incredibly challenging. NPSLE has diverse and highly heterogeneous clinical phenotypes, including headaches, psychiatric symptoms, and peripheral neuropathy [16]. The symptoms of NPSLE have been classified into 19 neuropsychiatric (NP) manifestations by the American College of Rheumatology (ACR). The defined 19 NP manifestations consisted of two major classifications: central nervous system (CNS) and peripheral nervous system. CNS manifestations are further divided into focal and diffuse [17]. These manifestations are listed in Table 1.

The prevalence of NPSLE in patients with SLE is 30–40%. Additionally, 50–60% of these develop NPSLE within one year of the SLE onset [18]. The prevalence of each type of NPSLE significantly differs according to the study design followed. These discrepancies might be due to the ambiguity in diagnosing NP symptoms, especially those non-specific to SLE, such as headache or mood disorders. Cerebrovascular disorders and epileptic seizures are found in 5–15% of patients with NPSLE. Cognitive impairment, mood disorders, acute confusional state, or peripheral neuropathy are found in only 1–5% of patients. In contrast, psychosis, myelitis, involuntary movements of the limbs and facial muscles, and aseptic meningitis are extremely rare. In Systemic Lupus International Collaborating Clinic Criteria (SLICC) proposed in 2012 for the classification of SLE, epileptic seizures, psychosis, mononeuritis multiplex, myelitis, peripheral neuropathy, cranial nerve disorders, and acute confusional state are defined as the NP manifestations of SLE. In contrast, other types of NP symptoms, such as headaches, mood disorders, and cerebrovascular disorders, are excluded due to their low specificity [19]. In 2019, new classification criteria for SLE were proposed by the European League Against Rheumatism (EULAR)/ American College of Rheumatology (ACR) [20,21]. In the new criteria, only delirium, psychosis, and seizure are defined as the NP manifestations to improve specificity for diagnosis with SLE.

Diagnosis

The numerous clinical symptoms of neuropsychiatric lupus (NPSLE) can complicate obtaining an accurate diagnosis. Standard neuropsychiatric features of systemic lupus erythematosus (SLE) encompass cognitive dysfunction, mood disorders, seizures, and psychosis, which can manifest as focal or diffuse and vary in severity, making diagnosis complex [22]. Diagnosing neuropsychiatric lupus typically involves a comprehensive evaluation, including clinical assessment, neuroimaging, cerebrospinal fluid analysis, and laboratory tests. Physicians often rely on established criteria, such as the American College of Rheumatology (ACR) criteria and the Systemic Lupus International Collaborating Clinics (SLICC) criteria, to aid in diagnosis and classification [23].

Given the mild, nonspecific symptoms of NPSLE, absence of specific diagnostic markers, overlap with typical symptoms, comorbid conditions, potential medication side effects, and symptoms occurring independently from SLE activity, various biomarkers are employed in the diagnosis and treatment monitoring of NPSLE [24]. These include autoantibodies like antineuronal, anti-ribosomal P, anti-NR2 antibodies, chemokines, cytokines, and intrathecal levels of PAI-1 and MMP-9. It is crucial to rule out conditions that mimic NPSLE symptoms, such as infections or metabolic disorders. CSF analysis, including interleukin-6 levels, plays a role in differential diagnosis [25,26].

Assessment for neuropsychiatric lupus should be personalized. While neuroimaging is beneficial, it has limitations. Traditional MRI suits localized symptoms, whereas functional imaging is better for demonstrating perfusion and neurometabolic changes. However, more than half of NPSLE patients exhibit regular brain MRIs. Single photon emission computed tomography (SPECT), measuring cerebral blood flow, can be more sensitive than MRI for NPSLE, although research results vary. Functional MRI (fMRI) is also employed to assess cognitive function in SLE [25,26]. Various classification criteria, such as the American College of Rheumatology (ACR) criteria, have been developed to assist in NPSLE diagnosis based on specific clinical and laboratory features. Magro-Checa et al. proposed a diagnostic approach for NPSLE that aligns clinical symptoms with specific diagnostic tests or procedures. At the same time, attribution models have been devised to enhance diagnosis, considering their limitations [25,27].

Cognitive function and psychological well-being assessments can provide valuable information for diagnosis. Without more reliable diagnostic tools, identifying neuropsychiatric symptoms due to SLE depends on the clinician’s judgment, suspicion, and clinical analysis. A comprehensive approach involving neuropsychological, radiological, laboratory assessments, and rheumatology evaluation enhances the accuracy of diagnosing NPSLE [24,29]. Distinguishing whether neuropsychiatric symptoms are directly caused by SLE or result from other factors like corticosteroid treatment or psychological burden is crucial for treatment decisions. Various models have been developed to enhance the identification of SLE-related neuropsychiatric symptoms [24,28]. Individualizing the diagnostic approach for each NPSLE patient is necessary because there’s no one-size-fitsall method. The diverse signs and symptoms require a diagnostic algorithm that can be applied to a broad range of cases [24,29].

Differential diagnosis

Neuropsychiatric manifestations of systemic lupus erythematosus can vary, so its differential diagnosis becomes a challenge. The neuropsychiatric signs and symptoms of SLE are often relatively nonspecific. They may share many standard features with well-established psychiatric disorders, including paranoid and grandiose delusions as well as auditory and visual hallucinations, hyperactive and hypoactive delirium, anxiety, and depression.

Mood disorders and anxiety are prevalent among the general population, and their occurrence is higher in individuals with chronic illnesses. Unsurprisingly, a significant percentage of lupus patients, precisely 15%, experience mood disorders, while 5% develop anxiety disorders [30]. A meta-analysis conducted in 2017 on 59 studies involving a certain number of adult SLE patients showed that some studies, which used reliable clinical interviews such as DSM and/or ICD, found that 24% of SLE patients had major depression while 37% of them suffered from anxiety [31]. A proportion of psychotic events in lupus are temporally related to corticosteroid use. However, such observations are likely to be confounded by increases in systemic disease activity, which might precede increased steroid dose [32].

In addition to primary neuropsychiatric disorders, other autoimmune diseases should be ruled out, including multiple sclerosis (MS), antiphospholipid syndrome (APS), and autoimmune encephalitis. MS can present with focal neurological deficits and cognitive impairment, while APS may cause cerebrovascular events similar to those seen in NPSLE. Autoimmune encephalitis, characterized by autoantibodies targeting neuronal antigens, can manifest as seizures, psychosis, and cognitive dysfunction, closely mimicking NPSLE [33,34]. Furthermore, infectious causes of neuropsychiatric symptoms, such as neurosyphilis, HIV-associated neurocognitive disorders, and viral encephalitis, should be considered. Neurosyphilis can present with a wide range of neurological and psychiatric symptoms, while HIV-associated neurocognitive disorders can lead to cognitive impairment. Viral encephalitis can cause seizures and altered mental status, resembling certain NPSLE presentations [35,36,38].

Structural brain lesions, including brain tumors, stroke, and vascular diseases, can also produce neurological symptoms akin to NPSLE. Imaging studies, cerebrospinal fluid analysis, and thorough neurological assessments are vital in distinguishing these conditions from NPSLE [35,39]. Moreover, medicationinduced neuropsychiatric symptoms should be considered, as certain drugs, such as corticosteroids or antiepileptic drugs commonly used to manage lupus, can lead to mood disturbances and cognitive changes [37,40].

Treatment strategies

Treating neuropsychiatric lupus, a complex facet of systemic lupus impacting the nervous system and cognitive function, demands careful consideration. This condition presents a diverse range of neurological and psychiatric symptoms, encompassing memory impairment, mood disorders, seizures, and, occasionally, psychosis. Given its multifaceted nature, a collaborative approach involving specialists such as rheumatologists, neurologists, and psychiatrists is often warranted to devise a tailored treatment strategy aligned with the patient’s specific clinical presentation [41].

The foremost objective in managing neuropsychiatric lupus centers on mitigating the underlying inflammatory and autoimmune processes, the condition’s root causes [41]. Mild symptoms have been alleviated with immunosuppressive agents such as azathioprine and mycophenolate [42]. Treatment regimens may incorporate immunomodulator agents like high-dose corticosteroids, intravenous disease-modifying antirheumatic drugs (DMARDs)-cyclophosphamide, or biologic therapies to temper the hyperactive immune response and diminish inflammatory activity [42]. However, it is pertinent to acknowledge that these medications may entail side effects, necessitating vigilant surveillance and meticulous side effect management. In cases characterized by recalcitrance or severe manifestations, therapies such as intravenous immunoglobulin (IVIG), plasmapheresis, or rituximab might be contemplated to alleviate the burden of pathogenic antibodies [42,43]. Additionally, antiplatelet and anticoagulation agents have also been recommended by the European League Against Rheumatism (EULAR) committee in patients who carry antiphospholipid antibodies to try to prevent a thrombotic episode [41].

Concurrently, addressing the neuropsychiatric symptoms constitutes a vital aspect of treatment [42,43]. Pharmacotherapy may include antidepressants or antipsychotics for mood disturbances, acute confusional states and psychosis, and antiepileptic drugs for seizure control. Biofeedback-cognitive rehabilitation therapy, complemented by cognitive-enhancing strategies, proves beneficial for individuals grappling with cognitive dysfunction [41]. Routine follow-up with healthcare providers is essential for assessing the efficacy of treatment, managing potential side effects, and fine-tuning the therapeutic regimen to optimize outcomes for patients navigating the complexities of neuropsychiatric lupus.

Prognosis & Outcomes

Little is known about the outcome of neuropsychiatric (NP) involvement in systemic lupus erythematosus (SLE). However, it is generally associated with a poorer prognosis. Hanly JG et al. (2020) found that neuropsychiatric events significantly decrease the quality of life and increase mortality in SLE patients, with a 16% risk of death over 10 years for those with SLE-related events [44]. A study published in Modern Rheumatology (2019) emphasized the correlation between the anti-ribosomal P protein antibody and a heightened risk of death in patients with diffuse SLE NP involvement (NPSLE) [45]. A report from Seoul identified that NPSLE, especially of the focal type in the central nervous system, triples the mortality risk [46]. Zirkzee and his team pinpointed a high mortality rate in patients with acute confusional states and those diagnosed with NPSLE at older ages [47]. Jönsen et al., analyzing a Swedish cohort, observed that while mortality didn’t show significant discrepancies, there was a pronounced work disability and a notable clinical impact of the neuropsychiatric manifestations in SLE patients compared to those without these manifestations [48]. Finally, Monahan et al. (2020) highlighted an increase in mortality in NPSLE patients compared to the general population, with infections being the leading cause of death [49].

Xue Li et al. (2019) outlined an overall survival of 89%, 85%, and 84% at 1, 3, and 5 years respectively, with a higher mortality in females. They also deduced that acute confusional states are linked to a worse prognosis, with a survival rate of 64% and 52% at 1 and 3 years, respectively. The latter, combined with elevated intracranial pressure (>250cmH2O), were independent prognostic factors for death [50]. According to another study by Shangzhu Zhang et al., a SLEDAI score >15, proteinuria, raised serum creatinine, and hypocomplementemia are independent prognostic factors for death [51]. In summary, systemic lupus erythematosus with neuropsychiatric manifestations (NPSLE) poses a challenging prognosis associated with diminished quality of life and heightened mortality. Despite identifying specific indicators, the comprehensive prognosis landscape calls for more detailed research.

Conclusion

Neuropsychiatric lupus, or neuropsychiatric systemic lupus erythematosus (NPSLE), represents a complex subset of systemic lupus erythematosus (SLE) characterized by central nervous system involvement. It encompasses a broad spectrum of neuropsychiatric symptoms that can significantly impact a patient’s quality of life. While NPSLE is relatively uncommon, its prevalence varies depending on diagnostic criteria and the population studied, affecting mainly women of childbearing age and those with more severe SLE manifestations. The pathogenesis of NPSLE is multifactorial, involving immune dysregulation, autoantibody production, and inflammation within the central nervous system. Autoantibodies like anti-phospholipid, anti- NMDA receptor and anti-ribosomal P antibodies may be crucial in developing neurological symptoms. The clinical presentation of NPSLE is highly heterogeneous, including cognitive impairment, mood disorders, seizures, and more, often challenging diagnosis and management.

Diagnosing NPSLE relies on clinical assessments, neuroimaging, cerebrospinal fluid analysis, and excluding other potential causes of neuropsychiatric symptoms. Various autoantibodies and biomarkers can aid in diagnosis, but it remains a clinical challenge. A multidisciplinary approach involving rheumatologists, neurologists, and psychiatrists is crucial for accurate evaluation. The treatment of NPSLE necessitates a tailored approach based on the specific neurological or psychiatric manifestations and their severity. Immunosuppressive therapies aim to target the underlying autoimmune and inflammatory processes, including corticosteroids, disease-modifying antirheumatic drugs (DMARDs), and sometimes biologic agents. Adjunctive therapies, such as antiepileptic drugs, antipsychotics, and antidepressants, may be required to manage specific symptoms. Regular monitoring and follow-up are essential to assess treatment response and adjust therapies as needed.

It is important to note that NPSLE poses a challenging prognosis, potentially decreasing the quality of life and increasing mortality compared to SLE without neuropsychiatric involvement. The prognosis varies based on the specific manifestations and individual factors, and further research is needed to understand the long-term outcomes better and improve management strategies for this complex condition.

To Know more about  Orthopedics and Rheumatology Open Access Journal

Click here: https://juniperpublishers.com/oroaj/index.php

To Know more about our Juniper Publishers

Click here: https://juniperpublishers.com/index.php

Wednesday, October 11, 2023

Snapshot of International Radıotherapy Center: Single Center Experience - Juniper Publishers

Cancer Therapy & Oncology  - Juniper Publishers


Abstract

Cancer can become anywhere in the human body almost including trillions of cells. Cancerous tumors spread or invade into the tissues to form new tumors that named as the process of metastasis. Radiation therapy (RT) was first used to treat cancer over a hundred years ago. The progress has been made to improve the effectiveness of this awesome modality and minimize side effects. RT also has been used with surgery, chemotherapy or immunotherapy in combined modality approaches for numerous malignancies to maximize tumor control while minimizing toxicity and preserving the organs and tissues. We intend to present our patient population whom delivering radiotherapy in our radiotherapy center. The data includes the patients who still delivering radiotherapy, initial or last day of radiotherapy. This article is about a snapshot of a treated patient population in one day at our center. Mean KPS (Karnofsky Performance Score) was 90 (70-100). 2 patients were in stage 1 (2%), 25 (28%) were in stage 2, 35 (39%) wee in stage 3 and remaining 23 (26%) were in stage 4. 4 (5%) of all were benign.

Keywords: Cancer; Radiotherapy; Experience; Single center

Introduction

Cancer is a disease that some body’s cells grow uncontrollably and spread to other regions of the body. Cancer can become anywhere in the human body almost including trillions of cells. What human cells do is to grow and multiply to form baby cells as the body requires them. If cells grow old or damaged, new cells take their place of died ones. In case this process breaks down, abnormal or damaged cells grow and may form tumors. Tumors can be cancerous or benign. Cancerous tumors spread or invade into the tissues to form new tumors that named as the process of metastasis. Cancerous tumors may also be malignant tumors. Benign tumors do not spread or invade the tissues. If they are removed, benign ones often do not grow back. Benign tumors can rarely be quite large which can cause serious symptoms or life threatening such as in the brain.

Radiation therapy (RT) was first used to treat cancer over a hundred years ago. The progress has been made to improve the effectiveness of this awesome modality and minimize side effects. RT also has been used with surgery, chemotherapy or immunotherapy in combined modality approaches for numerous malignancies to maximize tumor control while minimizing toxicity and preserving the organs and tissues. Multidisciplinary team of clinicians, including surgeons, medical oncologists, radiation oncologists, and other specialists determine the best approach for the indivualized treatment [1,2]. RT may be the sole treatment or be given concurrently with chemotherapy, or may precede or follow surgery to minimize the microscopic disease after treatment. Additionally, RT might be used palliatively for incurable cancers. The duration of RT can vary from a single shot to eight weeks of daily irradiation.

Randomized clinical trials have established similar outcomes between surgery and organ-preservation treatment with an RT for selected patients with prostate cancer, oropharyngeal cancer, breast cancer, laryngeal cancer and sarcoma, Some trials have shown the appropriateness of organ preservation for patients with bladder cancer and early-stage lung cancer. Definitive RT is a very important option for treating selected patients with potentially curable malignancies. In this original article, we intend to share our real data of single radiotherapy center with characteristics, doses, cancer types and treatment approach of all patients.

Materials and Methods

We intend to present our patient population whom delivering radiotherapy in our radiotherapy center. The data includes the patients who still delivering radiotherapy, initial or last day of radiotherapy. This article is about a snapshot of a treated patient population in one day at our center. Age, gender, diagnosis, stage, treatment, fraction size, radiotherapy device and Karnofsky Performance Score were collected from files as the patient characteristics. The radiotherapy devices in our center are tomotherapy (HI-ART) and linear accelerator (ELEKTA, UK).

Statistical Analysis

Statistical Package for the Social Sciences, version 26.0 (IBM Corp. Released 2019. IBM SPSS Statistics for Windows, Version 26.0. Armonk, NY: IBM Corp) software was used for analysis and the level of significance was set at P < 0.05. Descriptive statistics and survival analysis were applied. Survival analysis and curves were done via the Kaplan–Meier method. Survival curves were analyzed due to the T stage. Logrank test was used for the analysis of T stage survival curves.

Results

Total treated patients number is 89. 15 patients (17%) were treated with tomotherapy and 74 (83%) were delivered radiotherapy with linac. Mean age of population was 57 (12-83) years. 48 (54%) of all were females whereas males were 41 (46%). Mean KPS (Karnofsky Performance Score) was 90 (70-100). 2 patients were in stage 1 (2%), 25 (28%) were in stage 2, 35 (39%) wee in stage 3 and remaining 23 (26%) were in stage 4. 4 (5%) of all were benign. 83 (93%) of patient population were treated with conventional fractionation and 6 (7%) of all were treated with SBRT (Stereotactic Body Radiotherapy). 16 (18%) patients were delivered palliative doses and 73 (82%) of all were given curative doses. The diagnosis of patients was seem to be a wide range of different type of cancers. 24 patients (27%) were breast cancer, 5 (6%) of all were prostate cancer, 15 (17%) patients were lung cancer.

Head and neck cancer patients were 6 (7%) of all. 4 (4%) of all group were lymphoma whereas 2 (2%) patients were gynecological cancer. Gastrointestinal cancer patients were 12 (13%) of all. 3 (3%) of all population were skin cancer. Central nervous system cancer were in 3 (3%) patients whereas 2 (2%) of all were pediatric tumors. Benign patiens were 4 (4%) and CUP (carcinoma of unknown primary) patient was just 1 (1%). 8 remaining (11%) of all were diagnosed with other type of cancers.

Discussion

According to the data of International Atomic Energy Association, there are 8403 centers delivering radiotherapy. 15276 mv therapy and only 107 light ion therapy are used in these centers. The number of kv therapy devices are 740. 3380 brachytherapy devices are used for treatment. In Turkey, there are 137 centers for radiotherapy. 281 mv therapy devices are used here and no light ion devices are there in our country. The number of brachytherapy devices are 31.

RT is a treatment approach that delivers energy to kill malignant tumor cells in the targeted area. What RT do is to damage the DNA of cancer cell by ionizing the atoms making the DNA chain. An optimal balance must be achieved between probability of a radiation-induced complication in a normal tissue and the probability of tumor control. The therapeutic ratio is achieved by minimizing the dose to normal tissues or organs while maximizing the dose to the target. At the same time, the total dose of radiation is often divided (fractionated) into smaller daily doses to allow normal tissues to repair the radiation damage between treatments.

External beam radiation therapy (EBRT) is the most common RT approach which delivers the radiation from a source outside the patient [3]. Electrons are accelerated to high energy and are allowed to either exit the machine as an electron beam or to strike a target that produces X-rays (also known as photons), which are directed at the tumor in linear accelerators. Photons are the most widely used radiation mode due to their ability to penetrate deeply and reach internal organs whereas electrons are specifically used for superficial targets such as the skin and breast to minimize radiation to deeper tissues and organs. Treatment planning include definition of tumor target, patient immobilization, imaging, delineation of the target volumes and critical organs, consideration of dose and schedule, set-up and finally treatment.

Intensity-modulated radiation therapy (IMRT) is an ultimate form of 3- dimensional conformal radiotherapy (3D-CRT) that shapes the intensity of radiation in different parts of a single radiation beam while the treatment is delivered [4]. Image Guided Radiotherapy (IGRT) is real-time imaging of the treatment target and normal tissues during each treatment allows for minimization of additional margins and the reduction of irradiated volumes which decreasing missing a target. Particle therapy is a special form of EBRT, with protons being often used [5]. Proton radiation reduces the dose to normal tissues by allowing for more precise dose delivery because of the unique physical specialities of heavy particles [6]. Neutron RT is believed to have an advantage in the treatment of certain tumors such as recurrent or inoperable salivary gland malignancies or incompletely resected sarcomas of soft tissue, cartilage and bone [7,8].

Stereotactic radiation therapy techniques administer the calculated dose of radiation in one or a very limited number of treatment fractions. Stereotactic techniques often utilize photons that are delivered by a linear accelerator or by a cobalt-60 source. Stereotactic radiosurgery (SRS) refers to a single-fraction treatment of intracranial or spinal targets whereas stereotactic body radiation therapy (SBRT) meaning multifractional (typically two to five fractions) treatment of intracranial, spinal, or extracranial sites such as prostate, liver, pancreas, head and neck and lung [9,10].

Total body irradiation (TBI) is widely used as a component of preparative cytoreductive regimens for hematopoietic cell transplantation. Brachytherapy is a form of RT in which a radiation source is located inside or close to the area requiring treatment. The radiation emitted is usually active over only a relatively short distance. Brachytherapy can be delivered with either high dose rate (HDR) or a low dose rate (LDR) system [11,12]. Intraoperative radiation therapy (IORT) that single-fraction treatment used is the delivery method of radiation at the time of surgery and dose is limited by critical structures [13].

To Know more about  Cancer Therapy & Oncology International Journal

Click here: https://juniperpublishers.com/ctoij/index.php

To Know more about our Juniper Publishers

Click here: https://juniperpublishers.com/index.php

Cytotoxicity, Antimicrobial and Antioxidant Activities of Apocarotenoid Rich Leaf Essential Oil of Maesobotrya Barteri Var. Barteri (Baill.) Hutch - Juniper Publishers

  Technical & Scientific Research - Juniper Publishers Abstract Background: Maesobotrya barteri var. barteri (Phyllanthaceae) has anal...